Macular holes are a relatively uncommon condition, estimated to
occur in approximately 1 in 5,000 patients. Primary idiopathic macular hole is
an age-related condition, typically affecting individuals in their sixth and
seventh decades of life. Women comprise approximately 75% of affected patients.
The condition occurs bilaterally in 10% of patients but the onset is rarely
simultaneous. Most macular holes are idiopathic but a variety of other ocular
conditions have been associated with macular hole formation:
- Ocular trauma
- Best’s disease
- High myopia
- Histoplasmosis
- Epiretinal membrane
- Cystoid macular edema
- Proliferative diabetic retinopathy
- Rhegmatogenous retinal detachment
- Lightning trauma
- Nd:YAG laser injury
The exact pathogenesis of idiopathic macular hole remains
poorly understood. Currently, it is believed that abnormal tractional forces
from focal changes in the prefoveolar corticovitreous are primarily responsible
for idiopathic macular hole formation. The success of vitrectomy surgery for
idiopathic macular hole indicates a direct role of the vitreous in the
pathogenesis. Of the many systemic factors such as cardiovascular disease,
hysterectomy, hypertension, and serum fibrinogen levels, only elevated serum
fibrinogen levels appear to correlate with the increased risk of macular hole.
Symptoms from idiopathic macular hole formation
are typically noted incidentally on occlusion of the uninvolved eye or
routine ophthalmologic evaluation. Patients often complain of painless
central visual blur, with many patients complaining of metamorphopsia.
Central visual acuity correlates with the size of the hole initially but
tends to stabilize around the 20/200 to 20/800 level despite an increase
in hole diameter over time.
Clinically, the appearance of idiopathic macular hole is
recognized to progress through 4 stages. This classification scheme was first
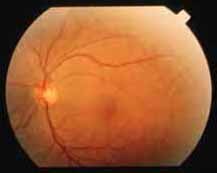
proposed by Gass in 1988 and later revised in 1995. The first stage, sometimes
termed a "premacular hole lesion," is noted biomicroscopically as a yellow
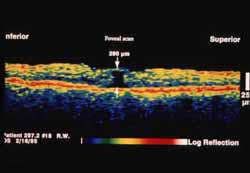
fovealor spot (stage IA) (
Slide 1) and possibly
represents serous foveal detachment from contraction of prefoveolar vitreous
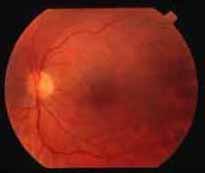
cortex. With further contraction, a yellow ring is noted clinically (stage IB)
(
Slide 2) and is believed to represent displacement of
photoreceptors, with their yellow xanthophyll pigment, peripherally. At this
stage a full vitreous retinal defect is present but is not visible through a
thickened and opaque prefoveolar cortex.
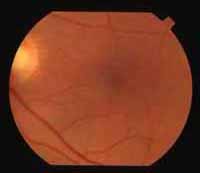
With further contraction of the prefoveolar vitreous, a hole in
the prefoveolar cortex forms and a full thickness retinal defect can be noted
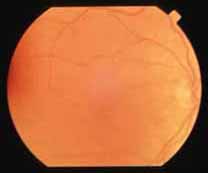
clinically; this is defined as a stage II (
Slide
3) macular hole.
The defect may be eccentrically located and measures less than
400 µm in size. A pseudo-operculum, which represents a condensed
vitreous, but not retinal tissue, may be noted anterior to the hole. Stage II
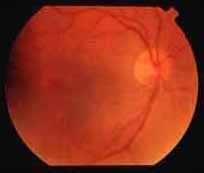
holes typically progress to stage III holes (
Slide
4).
In a stage III macular hole, the retinal defect enlarges to
more than 400 µm. Typically, a small doughnut-shaped cuff of subretinal
fluid is noted surrounding the hole. Fine yellow deposits may be noted at the
base of the hole. Perifoveal cystic retinal changes and a pigmented demarcation
line may be noted at the leading edge of the cuff of subretinal fluid. A stage
III macular hole progresses to a stage IV macular hole when complete
vitreofoveal separation occurs.
- Cystoid macular edema
- Vitreomacular traction syndrome
- Epiretinal membrane
- Macular pseudohole
- Pattern dystrophy
- Solar maculopathy
- Central serous retinopathy
- Foveal drusen
- Focal retinal pigment epithelium (RPE) depigmentation
The diagnosis of idiopathic macular hole is clinical. Slit lamp
biomicroscopy using a contact or non-contact lens is generally sufficient
although stage I and sometimes stage II holes can be difficult to detect. The
Watzke-Allen test is a commonly used diagnostic test that relies on subjective
input from the patient. A narrow slit beam is focused on the retina and is
centered over the macular hole. In a full-thickness macular hole, the slit beam
will appear to be interrupted. In conditions that mimic macular hole, the beam
is not interrupted and typically is not distorted. In early stages of macular
hole formation the slit beam does not appear to be interrupted but may appear
distorted or indented. The subjective nature of this test may limit its use.
Abnormalities in a number of psychophysical tests have been
noted in eyes with full-thickness macular holes. Evoked visual potentials using
small checks are believed to be the result of macular stimulation. These
potentials have been found to be reduced in eyes with macular hole. The focal
electroretinogram is diminished in eyes with full-thickness macular hole.
Perimetry with the scanning laser ophthalmoscope can demonstrate absolute
scotomata in the area of neurosensory defect as well as relative scotomata in
the area of neurosensory detachment surrounding the macular hole.
Fluorescein angiography while nondiagnostic, may be useful in
some patients with macular hole, primarily by excluding other disease entities
that may mimic macular hole. In stage I macular holes, fluorescein angiography
is typically normal. In a stage II macular hole, a small window defect
corresponding to the area of macular hole formation may be seen. Some stage II
macular holes demonstrate intense hyperfluorescence in the window defect while
others appear to have a normal study. Stage III and IV macular holes
demonstrate mildly hyperfluorescent window defects that also correspond to the
area of macular hole formation.
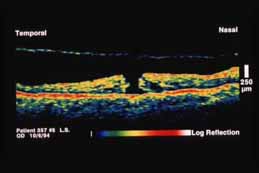
Optical coherence tomography (OCT) has proven to be extremely
useful in the diagnosis of macular hole. OCT is able to clearly delineate early
stage macular holes and provides exquisite detail of the vitreoretinal
relationship. Stage IA macular holes demonstrate oblique vitreous traction and
secondary cystic foveal changes. Occult stage IB lesions can be clearly imaged
(
Slide 5). Stage II, III, and IV lesions demonstrate
full thickness defects. The ability of OCT to measure the transverse size of
the macular hole further adds to the utility of this diagnostic modality. In
stage IV holes, the overlying detached posterior hyaloid can sometimes be
imaged (
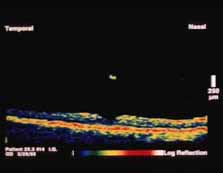
Slide 6). OCT can also differentiate true
macular holes from similar lesions such as lamellar holes (
Slide 7A and
Slide 7B).
Vitreous surgery may improve visual acuity in some eyes with
recent onset macular hole formation. Since 1989, vitrectomy has become the
largely accepted and performed procedure for this condition. Generally,
operating on eyes with stage I macular holes is not preferred because there is
a 50% rate of spontaneous resolution and an intraoperative macular hole may
form. The success rate of vitrectomy for stage II macular holes is over 90%.
The Vitrectomy for Treatment of Macular Hole Study Group, a
prospective, randomized, controlled study, demonstrated improvement in
potential acuity meter testing following surgery for stage II, III, and IV
holes but only marginal benefits on Early Treatment Diabetic Retinopathy Study
vision testing. It is believed that formation of postoperative cataract may
have confounded the visual assessment by the latter method.
Vitrectomy with air fluid exchange, injection of a dilute
mixture of a long-acting gas, and possible membrane peeling is the procedure of
choice. The surgery is typically performed under local anesthesia. The
following steps are generally performed:
- Standard 3-port vitrectomy
- If a posterior vitreous detachment is not
present, the posterior cortical vitreous is engaged using the vitreous
cutting instrument, silicone tipped extrusion needle, a bent needle,
or pick and elevated off the retina. The remainder of the posterior
vitreous is resected.
- Epiretinal membrane peeling or internal
limiting membrane peeling may be performed at this point using a bent,
sharp needle.
- Air-fluid exchange is performed.
- Adjunctive agents, if used, are applied.
- Dilute sulphur hexafluoride (SF6) or
perfluoropropane (C3F8) gas is placed into the vitreous cavity and the
sclerotomy sites are closed.
- Face down positioning is recommended for 7 to 10 days.
The most common complication of surgery for macular hole is
cataract formation with over 50% of eyes developing significant nuclear
sclerosis over a 2-year follow-up period. Retinal detachment and retinal tear
can occur in up to 10% of eyes undergoing surgery. The high incidence may be a
result of the intraoperative creation of a posterior vitreous detachment. Other
complications include light toxicity to the retinal pigment epithelium, late
reopening of macular holes, intraoperative enlargement of the macular hole, and
endophthalmitis. The most controversial aspects of vitrectomy for macular hole
include the use of adjuvants such as autologous serum or transforming growth
factor beta, the necessity of internal limiting membrane peeling, the necessity
of prone positioning, the extent of tamponade, and concomitant cataract
surgery. The use of adjuvants may be falling out of favor due to the high
success rates without the use of these agents and the inability to reproduce
the initially reported success rates with some of these agents.
Currently, there is a trend toward shorter acting gases and
shorter prone positioning times as several uncontrolled studies suggest that
long-term tamponade and positioning may not be essential for success. Some
surgeons prefer to peel the internal limiting membrane during surgery for
macular hole but the benefit of this removal is unproven.