Reprinted with permission from Rothman RF, Liebmann JM, Ritch R. Incisional treatment of glaucoma. In: Sassani J, ed. Ophthalmic Fundamentals: Glaucoma. 2000:205.
Introduction
It has been known that elevated intraocular pressure (IOP) is a significant risk factor for the development of glaucomatous optic neuropathy and visual field loss,1-5 and that reducing the IOP in patients at risk can preserve visual function.6-10 Although ophthalmologists have known about this association between elevated IOP and glaucoma since the early 1600s, surgical attempts at lowering the pressure did not originate until the 1800s when MacKenzie performed both a sclerotomy and paracentesis, which transiently lowered the IOP.11-14
The goal of filtering surgery for glaucoma is the creation and maintenance of a patent fistula from the anterior chamber to the subconjunctival space. The indications for performing glaucoma surgery are complex and varied. Although different procedures and techniques will be discussed in this chapter, the unifying goal of all procedures is to lower IOP to preserve visual function.
Generally, incisional glaucoma surgery is performed on patients for whom medical or laser therapy has failed to control IOP. Factors that influence the choice of surgical technique include disease severity, the desired pressure reduction, and the patient's quality of life.15-17 The long-term application of topical antiglaucoma medications has been reported to reduce the success of filtration surgery.18-21 Therefore, earlier surgery may be indicated in certain patients.22-25 The Collaborative Initial Glaucoma Treatment Study, is a nationwide, prospective, randomized clinical trial sponsored by the National Eye Institute comparing the outcomes of newly diagnosed open-angle glaucoma patients treated initially with either medication or surgery. This study will help determine the relative risks of early surgery. This tutorial provides clinicians with an overview of incisional glaucoma surgery from the preoperative evaluation to the management of postoperative complications.
Surgical Decision Making
As with any surgery, the preoperative evaluation of the glaucoma patient is a multifaceted process that may span many patient visits or occur at a single examination. The patient's diagnosis (i.e., type of glaucoma), previous surgical history, severity of disease, target IOP, and the status of the fellow eye are important factors in patient assessment. A thorough investigation should be made to determine the extent of glaucomatous optic neuropathy and visual field loss, loss of functional ability, and the rate of disease progression.
Once the decision to perform surgery has been made, a careful history and examination must be performed so that the appropriate procedure can be planned. Factors that have been reported to affect the outcome of glaucoma surgery include young age, black race,26-28 glaucoma diagnosis,29-39 and previous surgical history.40-43 For example, older patients have a higher success rate than younger ones44-47 due to a less intense fibroproliferative reaction and healing response. African-Americans appear to respond less favorably to standard filtering surgery due to increased scarring of the conjunctiva and Tenon's capsule.48-50 Although the success rate of filtration surgery is high for patients with chronic, noninflammatory open-angle or angle-closure glaucoma who have not undergone previous surgery, a history of previous incisional surgery, neovascular glaucoma, or inflammation decreases surgical success. Each of these factors must be considered when contemplating surgical intervention.
The preoperative surgical examination begins with an assessment of the conjunctiva and periocular tissues. Conjunctiva that is scarred from cicatricial disease or previous incisional surgery may be difficult to manipulate for creation of a filtration bleb or may suggest the use of a fornix-based rather than a limbus-based conjunctival flap. Severe conjunctival scarring may preclude successful filtering surgery. Eyes that have significant peripheral anterior synechiae may require an anterior placement of the sclerostomy, or an alteration in the position of the surgical site to enhance success. The presence of active inflammation or neovascularization often leads to a decision to perform surgery that relies less on the presence of healthy conjunctiva (i.e., tube-shunt implantation). Adjunctive antifibrosis may be applied both during and after trabeculectomy in high-risk patients or when a low postoperative IOP is desired.
Necessary information to be identified during the examination includes the presence of concomitant ocular disease. Conditions such as cataract often cause an alteration in the choice of procedure. Combined cataract and glaucoma surgery may eliminate the need for multiple trips to the operating room while maximizing visual rehabilitation. Patients who require concomitant vitrectomy may undergo implantation of an aqueous tube-shunt into the vitreous cavity rather than the anterior chamber.
Once the history and examination have been completed, an assessment must be made as to the overall prognosis of the eye. Eyes with severely elevated IOP and poor visual potential should be managed with less invasive procedures, if possible. These eyes often respond to single or multiple attempts at ciliary body ablation with cyclocryotherapy or cyclophotocoagulation.
Preoperative Preparation
Informed consent must be obtained prior to surgical intervention and should include a discussion of the risks, benefits, and alternatives of the planned procedure. The discussion should be in language understandable to the patient, and all questions regarding the preoperative, operative, and postoperative routine should be answered. This includes both minor and major risks of the surgical procedure, postoperative restrictions, and anticipated medical regimen. This discussion should not be rushed and should be carried out by the person who will be performing the surgery.
It is often necessary for patients to discontinue certain medications prior to undergoing glaucoma surgery. Oral anticoagulants such as warfarin, persantine, and aspirin should be discontinued if possible. Effective anticoagulation can lead to hyphema from iris manipulation or even suprachoroidal hemorrhage from a precipitous drop in IOP. These medicines should not be discontinued if discontinuation poses significant risk to the general health of the patient.
For patients who can tolerate a short period of IOP elevation, it is often advantageous to discontinue certain topical antiglaucoma medications, as well. Long-acting miotics such as echothiophate iodide and demecarium bromide should be discontinued a minimum of 2 to 4 weeks prior to surgery with planned general anesthesia because of the potential systemic interaction between these medications and medications used during general anesthesia.51 These topical agents have been shown to deplete plasma pseudocholinesterase, which is also responsible for the degradation of succinylcholine, a medication commonly used to induce paralysis prior to intubation during general anesthesia administration. Therefore, patients may experience prolonged muscle relaxation, respiratory depression, and apnea if succinylcholine is used in the presence of these agents.52
Aqueous suppressants should be continued until the day of surgery. This is especially true for patients with advanced glaucomatous optic neuropathy who are at risk for losing fixation due to an IOP rise. Miotics cause a breakdown in the blood-aqueous barrier and promote inflammation.53-55 Discontinuing miotics prior to intraocular surgery may decrease the amount of postoperative inflammation. If concomitant cataract or other intraocular surgery that requires an adequate view of the posterior segment is planned at the time of glaucoma surgery, discontinuation of miotics may also facilitate pupillary dilation. In addition, the prolonged stimulation of the ciliary body and pupillary sphincter induced by miotics can be counterproductive when attempting to manage a shallow anterior chamber or malignant glaucoma. Epinephrine agents should be discontinued because of their effects on conjunctival vasculature.
Generally, patients who are scheduled for intraocular surgery should have a physical examination and provide a general medical history preoperatively.56-58 Even with the advent and implementation of topical anesthesia, intravenous (IV) sedation usually is administered regardless of the procedure. The presence of concomitant medical problems such as hypertension, diabetes, cardiac disease, and pulmonary disease is significant in terms of anesthetic and sedative risk, and surgical positioning and tolerance. It is imperative that the ophthalmologist be aware of the medical status of his or her patient. Other medical problems that require the use of systemic medications for control also are important. Patients who regularly use anticoagulants or steroids often have adjustments made to their medical regimen prior to surgery in an attempt to correct for possible missed doses and to overcome the stress that surgery places on the body.
Many surgeons prescribe broad spectrum topical antibiotics for several days prior to intraocular surgery. Others use several drops 1 or 2 hours prior to the procedure. Nevertheless, several studies have shown that the only medication that causes a statistically significant reduction in the incidence of early postoperative endophthalmitis is topical 5% povidone-iodine used as a preoperative wash.59,60
Anesthesia
In glaucoma surgery, general anesthesia is used primarily for
infants and children. It also is appropriate, however, for adult patients who
are unable to remain in a comfortable lying position due to musculoskeletal or
respiratory difficulties, extremely nervous, confused, or unable to cooperate
under local anesthesia.61-64 Other advantages of general anesthesia
include elimination of the risk of orbital or ocular complications from the
local anesthetic and creation of better operating conditions for the surgeon.
Ocular effects of inhalation anesthesia include a significant rise in IOP
during endotracheal intubation65,66 and a possible role in the
formation of delayed suprachoroidal hemorrhage due to increased episcleral
venous pressure, which occurs during extubation or secondary to postoperative
nausea and emesis.67
Retrobulbar, peribulbar, subconjunctival, or topical anesthesia may be considered for glaucoma surgery.68,69 Some clinicians believe that retrobulbar anesthesia should be avoided, if possible, because of its many associated complications. It has been shown that the potential exists for a sudden, often extreme elevation of IOP that can occur with retrobulbar injection.70,71 The fluid bolus may also cause direct compression of the optic nerve or its blood supply. Finally, the risk of retrobulbar hemorrhage, which also can compromise the optic nerve, and the risk of ocular perforation are alleviated.69,72-75 Dilute concentrations of epinephrine used in an attempt to enhance the efficacy of local anesthesia should not be included and may be harmful to patients with advanced glaucoma. The vasoconstriction caused by epinephrine not only counteracts the vasodilatory effect of local anesthetics, but also, theoretically, may compromise optic nerve blood flow.
Although peribulbar anesthesia is generally considered to be safer than retrobulbar anesthesia, the increased volume of fluid administered in the peribulbar space may be associated with slightly higher postinjection IOPs.76 Sub-Tenon's anesthesia has little associated risk and has been shown to be efficacious in patients undergoing trabeculectomy.72 In addition, by injecting anesthesia into the sub-Tenon's space superiorly, the associated fluid dissection can facilitate the creation of limbus-based conjunctival flaps. Finally, topical anesthesia can be used in patients who are able to cooperate during the planned procedure or at increased risk from the administration of other types of anesthesia. It also should be mentioned that regardless of the type of ocular anesthesia used, we perform a lid block in nearly every case to avoid blepharospasm during the procedure.
Surgical Technique
Trabeculectomy
Trabeculectomy is indicated
in most patients with glaucoma who require a lowering of their IOP but IOP
lowering is not attainable with the use of medication or laser therapy.
Surgical Exposure
Adequate exposure is critical for
glaucoma surgery, particularly if a limbus-based conjunctival flap is planned.
Achieving such exposure involves properly placing a sterile eye drape to remove
the lashes from the surgical field and using an appropriately sized lid
speculum that exerts minimal pressure on the globe. In an effort to have more
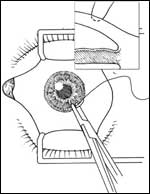
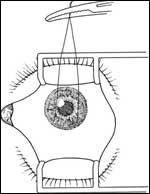
control over the eye during surgery, we routinely place a corneal traction
suture instead of a superior rectus bridle suture. This technique involves
placing an 8-0 Vicryl suture on a cutting needle to the depth of the
mid-corneal stroma for approximately 3 mm at the limbus directly anterior to
the proposed scleral flap (Slide 1A and
Slide 1B). The suture is then placed on gentle
traction inferiorly. This suture allows for excellent control of eye movement
during surgery and prevents rectus muscle hemorrhage, most cases of
postoperative ptosis,77,78 and the diplopia79 that can
occur with bridle sutures.
Conjunctival Flap
Creation of a conjunctival flap
is critically important during glaucoma filtering surgery. Either a fornix-or
limbus-based approach can be used because both have been shown to produce
similar results in eyes not receiving adjunctive antifibrosis
therapy.80-84 If a limbus-based flap is to be used, the entry should
be 8 mm to 10 mm posterior to the limbus to avoid placing the conjunctival
incision over the scleral flap (Slide 2). The
conjunctiva should be grasped with anatomic or non-toothed forceps
approximately 12 mm posterior to the limbus and elevated off of the eye. The
assistant should grasp the tissue approximately 1 mm to 2 mm anterior to the
surgeon to create a tent in the conjunctiva. Blunt Westcott scissors are then
used to incise the conjunctiva parallel to the limbus for approximately 10 mm
to 15 mm. The same procedure is repeated for the incision of the Tenon's
capsule. The incision through Tenon's capsule and down to episclera should be
at a point anterior to the conjunctival incision. Blunt dissection should be
performed to reach the conjunctival insertion at the limbus. Tenon's capsule
may be relaxed with circumferential incisions to permit adequate exposure.
These relaxing incisions make exposure of the surgical limbus much easier.
However, care must be taken to avoid accidental incision of the conjunctiva.
When performing these dissections, both the surgeon and the assistant should
try to grasp only Tenon's capsule when possible for traction. The conjunctiva
should not be handled, if possible. Once the dissection has reached the limbus,
episcleral tissue should be gently removed by scraping the sclera with a
surgical blade. Hemostasis should be obtained prior to the scleral incision
with cautery utilizing a fine tip (0.25 mm) to minimize tissue contraction and
shrinkage.
The procedure for creation of a fornix-based conjunctival flap is technically easier than creation of a limbus-based flap (Slide 3). A peritomy encompassing approximately 2 clock hours is made at the limbus with sharp scissors while grasping the tissue with anatomic or non-toothed forceps. The sub-Tenon's space is then entered with blunt dissection. Again, care must be taken to avoid tearing or macerating the free conjunctival end so that a watertight closure can be performed. The technique for cautery and exposure of the scleral bed are identical to that for the limbus-based flap. The decision to perform either a limbus- or fornix-based flap is one of surgical exposure, anatomy, and surgeon's preference.
Scleral Flap
After the scleral bed has been
prepared, the globe should be stabilized with a toothed forceps and the outline
of the scleral flap should be created (Slide 4). A
one-half thickness scleral flap then should be dissected into clear cornea
utilizing a lamellar technique. If an antifibrosis agent applied with an
intraoperative sponge is to be used, at this time, it can be placed on the eye
between Tenon's capsule and the scleral flap and allowed to remain for the
predetermined period. After the sponge has been removed and copious irrigation
performed, the procedure can continue. Care must be taken not to shred the flap
during manipulation.
Paracentesis
Following the scleral flap dissection,
a paracentesis should be made in the temporal peripheral cornea. This incision
provides access to the anterior chamber for intra- and postoperative management
of anterior chamber depth and IOP. Irrigation through the paracentesis aids in
assessment of the outflow pathway. Conjunctival wound leaks and buttonholes
also can be detected. If possible, the paracentesis should be placed so that
the internal entry is over the iris and the wound angled toward the 6 o'clock
position so that instrumentation placed into the eye will not cross over the
pupil and lens.
Sclerostomy
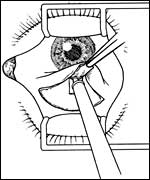
For creation of the internal ostium (Slide 5A and Slide 5B), the
globe is grasped with toothed forceps adjacent to the scleral flap while the
assistant gently lifts the flap out of the way. The anterior chamber should be
entered at the base of the scleral flap and an internal section of clear cornea
with or without trabecular meshwork should be excised with a knife or punch.
The scleral flap should be able to fully cover the entire internal ostium.
Iridectomy
An iridectomy is performed in nearly all
trabeculectomies. The purpose of an iridectomy is to prevent iris from
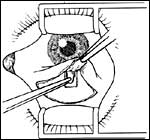
incarcerating into the internal ostium. The iris tissue is grasped with
small-toothed forceps through the sclerostomy while the assistant gently lifts
the scleral flap (Slide 6A and Slide 6B). The role of the assistant is critical at this
time because adequate exposure must be obtained while taking care not to
distort the wound, which might result in excessive aqueous outflow and anterior
chamber shallowing. The size of the iridectomy should be larger than the
sclerostomy at its basal aspect and should not extend centrally. The iris
tissue then is reposited into the eye with irrigation. The excised iris
specimen should be examined to ascertain that a full-thickness piece of iris
was removed. Gently rubbing the specimen against the surgical drape produces a
dark streak of pigment if full-thickness iris tissue is present. If there is a
small amount of bleeding from the iris root, it usually stops spontaneously
within a few minutes.
Prolonged bleeding may require instillation of viscoelastic into the anterior chamber for tamponade. Cauterization rarely is necessary and should only be performed in extreme cases of prolonged bleeding that is not responsive to conservative measures. The anterior chamber should be reformed with balanced salt solution as necessary.
Scleral Flap Closure
The scleral flap should be closed
promptly and with little distortion of the globe. Excessive flow through the
ostium can result in significant anterior chamber shallowing. Two or three
nylon sutures usually suffice to reapproximate the scleral flap to the scleral
bed (Slide 7). The eye should be inflated with
balanced salt solution to an appropriate IOP prior to securing the knots. Once
the first suture is placed, the remaining sutures should be placed with similar
tension. A notation should be made as to which is the tightest suture for
subsequent laser suture lysis. Flow should be assessed again and the sutures
adjusted, removed, and replaced as necessary to be certain that the flow rate
is adequate.

Conjunctival Closure
Once the scleral flap is
secure and the anterior chamber is of appropriate depth, conjunctival closure
can be performed. Careful creation of a watertight seal helps prevent
postoperative hypotony. Leakage at the wound edge predisposes to hypotony and
its associated complications, delayed wound closure, and formation of localized
blebs with poor pressure control. Many sutures and techniques for conjunctival
closure have been described. When closing a limbus-based flap, we use either
9-0 polyglactin in a running and locked fashion or 10-0 nylon with a running,
mattress technique (Slide 8). Non-toothed forceps are
used to approximate the wound edges and relax any tension that may have
developed from tissue retraction. The suture is then placed through both sides
of the wound at one end and tied with a surgeon's knot (3:1:1). When using
polyglactin, the suture is placed from the anterior to posterior wound edges
and reverse locked to secure the tension. Each throw should be placed
approximately 0.5 mm apart for the entire length of the wound. The suture is
then tied at the distal end and cut long enough so as not to cause lid
irritation. In an attempt to create a more watertight closure, Tenon's capsule
should be incorporated into the closure on the posterior aspect of the wound.
This also helps to prevent anterior migration of the wound. A nonlocking
mattress suture technique should be used with nonabsorbable sutures because it
is tedious to remove a locked suture.
Closure of a fornix-based flap involves reattaching the conjunctiva to its limbal insertion. This is accomplished by placing a 10-0 nylon suture on a vascular needle through the conjunctiva and Tenon's fascia on its posterior surface and then distally through the cornea, back toward the scleral flap, and out the corneal tissue (Slide 9). The needle should be placed mid-stroma through the cornea and the bite should be at the peripheral limbus and approximately 2 mm long. By passing the suture in this manner, the knot can be moved to a location beneath the conjunctiva, reducing subsequent corneal irritation. Some surgeons debride the corneal epithelium to enhance adherence of the conjunctiva or place an additional nylon suture in a mattress fashion centrally.
Once watertight closure has been achieved, the anterior chamber should be reformed with balanced salt solution to an appropriate IOP and the degree of flow through the sclerostomy assessed. The bleb should be checked with a fluorescein strip to detect for the presence of leaks, which should be closed before leaving the operating room. A subconjunctival injection of antibiotic and steroid usually is given in a location opposite the filtering site and additional combination antibiotic/steroid ointment is placed on the eye. A gentle patch is placed on the eye, which is taped shut and covered with a protective (e.g., Fox) shield.
Full-Thickness Procedures
Prior to the
advent of trabeculectomy, full-thickness procedures were routinely performed in
the surgical management of glaucoma. The creation of a direct channel from the
anterior chamber to the subconjunctival space was extremely effective at
lowering IOP, but was associated with significant complications including
hypotony, flat anterior chambers, ciliochoroidal detachments, endophthalmitis,
and cataract formation.47,85,86
All full-thickness surgeries share the similar feature of the creation of a direct channel for free-flow of fluid from the anterior chamber to the subconjunctival space. The procedure for posterior lip sclerectomy87,88 involves creating a circumlinear incision of approximately 3 mm in length with a sharp knife immediately posterior to the conjunctival insertion. A punch is then used to take several pieces of full-thickness sclera from the posterior lip of the wound so that the approximate size of the sclerotomy is 1.5 mm to 2 mm long by 1 mm wide. A peripheral iridectomy then is performed followed by conjunctival closure.
Thermal sclerostomy89-93 is a variation of posterior lip sclerectomy in which cautery is used to outline the linear incision in the sclera, which overlies the anterior chamber. Alternating cautery and sharp incisions are used to penetrate the eye wall. The heat of the cautery causes tissue contracture and mild gaping of the wound, which allows for free flow of fluid from the eye.
Iridectomy for Angle Closure
The primary
indication for performing iridectomy is to relieve angle-closure glaucoma due
to pupillary block. Since the advent of both argon and Nd:YAG lasers, surgical
iridectomy has become supplanted by these newer, noninvasive, and lower cost
techniques.94-96 In rare cases, however, in which an inadequate view
of the anterior segment and iris (e.g., corneal edema) precludes successful
laser treatment, surgical iridectomy may be indicated. In addition, one might
perform an iridectomy as a primary procedure to remove a possible malignant
iris lesion or to perform a biopsy.97 With the exception of these
two indications, iridectomy almost always is performed as part of another
intraocular procedure.
Peripheral iridectomy involves the removal of a small piece of iris tissue from an area outside of the visual axis and, preferably, beneath the eyelid. A sector iridectomy involves the removal of a pie-piece shaped segment of iris tissue, which includes the iris sphincter and pupillary margin. Sector iridectomies have been advocated for enlargement of a miotic or corectopic pupil that inhibits adequate light from falling on the retina, or for removal of iris lesions. Complications of sector iridectomy include photophobia, glare, and hyphema.
Although a limbal incision can be used, a clear corneal incision is preferable to preserve conjunctiva for future filtering surgery. In creating the limbal wound, a conjunctival peritomy is made superiorly followed by the creation of a 2-mm to 3-mm beveled incision at the surgical limbus (Slide 10). This is analogous to a miniature cataract wound. If a clear corneal wound is to be placed, the 3-mm incision should be made perpendicular to the corneal plane just anterior to the limbus and central to the limbal arcade. In both cases, the groove should be beveled. The wound should be placed to facilitate performing a basal iridectomy, which is less visually significant and less likely to be occluded by synechiae from the iris to the lens.
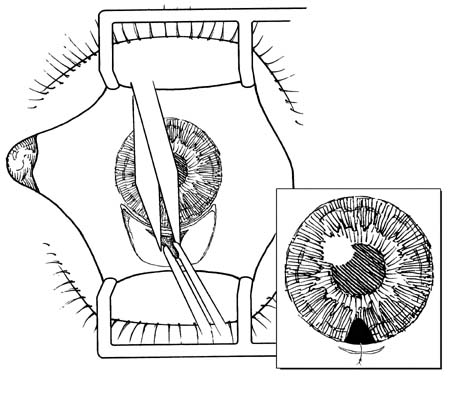
After removal of a full-thickness iris specimen, the wound is then closed with a single or multiple 10-0 nylon sutures with rotation of the knot into the tissue to avoid irritation. The wound should be watertight. The conjunctiva can be closed separately with an absorbable suture if a limbal wound was used. If the anterior chamber shallowed during the procedure, it is best to reform it prior to suture placement to avoid overly tight sutures. The procedure is completed with subconjunctival injections of steroid and antibiotic followed by placement of a cycloplegic agent to help prevent ciliary spasm, synechia formation, and malignant glaucoma. Patients then can be placed on a standard regimen of frequent topical steroids, antibiotics, and cycloplegics during the postoperative period.
Complications of surgical iridectomy include bleeding and hyphema, flat anterior chamber from wound leakage,98,99 malignant glaucoma, and failure to perform a complete iridectomy with persistence of pupillary block. Late complications include photophobia, glare and diplopia from large iridectomies,100 cataract formation,101-103 and subconjunctival fistula formation. Finally, all of the associated risks of intraocular surgery including endophthalmitis, wound incarceration, and vitreous loss must be considered.
Cataract and Glaucoma
The first step in the
management of coexistent cataract and glaucoma is to determine the choice of
surgical procedure. In patients who have early optic neuropathy and good IOP
control, cataract extraction alone might be appropriate with monitoring of the
IOP postoperatively. In patients with moderate to severe glaucoma who also have
a visually significant cataract a combined procedure (one-site or two-site)
often is indicated.104-109 Finally, for patients with uncontrolled
IOP and advanced visual field loss, a staged procedure (trabeculectomy first to
allow for stabilization of the IOP followed by cataract extraction at a later
date) can be considered. The indications for performing cataract extraction are
a topic beyond the scope of this tutorial.
The preferred method of cataract extraction to be used in combination with trabeculectomy is phacoemulsification.110-112 The smaller wound size promotes less inflammation and allows for greater success of the trabeculectomy. We usually use a fornix-based conjunctival flap, although many surgeons use limbus-based flaps.113,114 After creation of the conjunctival flap and preparation of the scleral surface, a linear incision is made in the sclera approximately 2 mm posterior to the limbus. The length of this incision should be long enough to accommodate both the phacoemulsification handpiece and the proposed intraocular lens. Dissection with a crescent blade then is carried into clear cornea just beyond the limbal arcade using a lamellar technique. Particular attention should be directed to the thickness of the corneoscleral flap. If an antifibrotic agent is to be used, it is applied at this time. An effort should be made to avoid having the sponge contact the limbal conjunctiva as this may predispose to wound leakage. After the sponge is removed and thorough irrigation is performed, a paracentesis is made for placement of the second instrument used during phacoemulsification. A keratome then is used to enter the anterior chamber through the corneoscleral wound.
Occasionally, patients who have been on miotics for an extended period or who have a history of inflammatory eye disease have an extremely miotic pupil that precludes adequate access to the lens. In these patients, freeing of the posterior synechiae with an iris sweep and placement of viscoelastic over the pupil may enlarge the opening enough for lens removal. If this is not sufficient, pupil stretching can be performed by placing two iris hooks through the wound and directing force both inferiorly and superiorly to physically open the pupil (Slide 11A and Slide 11B). The same procedure is then performed nasally and temporally by placing one of the hooks through the paracentesis. When this procedure is not sufficient, we often use iris retractors to artificially create a larger pupil.115 Four small retractors are placed through stab incisions at the 10, 2, 4, and 8 o'clock positions and effectively create a square pupil (Slide 12A and Slide 12B). If iris retractors are not available to stretch the pupil, small sphincterotomies created with scissors often suffice.116 Cataract extraction then is performed in the usual fashion.
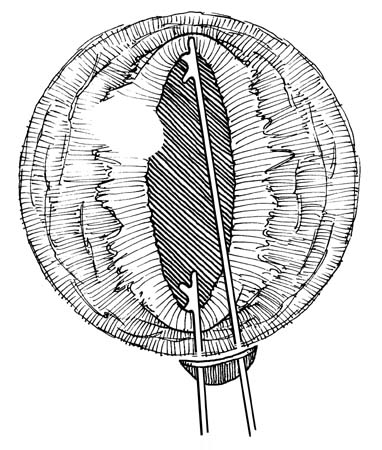
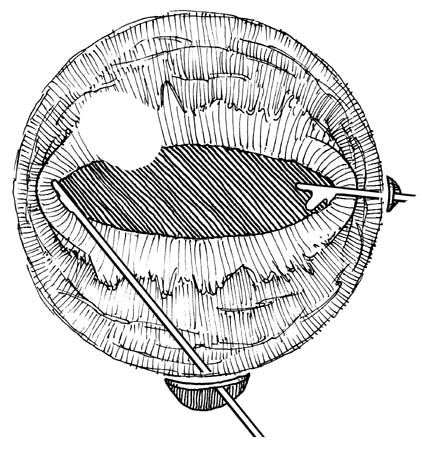
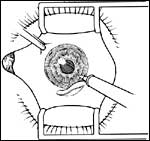
Emphasis should be placed on thorough cortical clean-up and removal of all nuclear fragments because any residual lens material incites a significant inflammatory reaction, which may jeopardize the success of the filtration procedure. Lens insertion can be performed after the anterior chamber and capsular bag are inflated with viscoelastic. Once this procedure is complete, a Kelly-Descemet punch is placed into the corneoscleral wound and a sclerostomy is performed with several bites to create a round opening. An iridectomy is then performed as usual and the posterior aspect of the wound closed with 10-0 nylon sutures as necessary. If additional filtration is required, some surgeons create winged incisions at the lateral aspect of the scleral flap to create a more standard scleral flap, rather than a linear incision, and place their scleral flap sutures appropriately. If the method of cataract extraction must be converted to a standard extracapsular technique, this can easily be performed by extending the linear incision toward the limbus with a beveled blade and opening the tissue with corneoscleral scissors. The sclerostomy should be performed as usual at the conclusion of the case and meticulous suture technique must be used to avoid leakage from the wound. This should be confirmed with irrigation through the paracentesis.
Glaucoma Implants
In cases in which
satisfactory filtration surgery may not be possible due to poor quality
conjunctiva, glaucoma implants offer a viable option. These devices are
designed to reduce IOP by shunting aqueous through a tube to an encapsulated
area surrounding an explant located on the scleral surface approximately 10 mm
posterior to the limbus. The history of attempting to drain aqueous through a
tube has led to the modern surgical device. Although there are many styles of
drainage implants,117-122 all modern devices consist of a silastic
tube attached to an external reservoir. Because the major determinant of IOP
reduction with these devices is the resistance of the capsular wall to aqueous
flow at the explant site,123-125 surface area is of critical
importance. Larger plates allow for a greater area of encapsulation and,
theoretically, lower IOP,118,126-128 although this relationship is
not a direct one. The main difference among the currently available devices is
the presence or absence of a valve designed to limit the flow of aqueous. The
presence of a valve mechanism in the Krupin and Ahmed implants allows for
restriction of flow particularly in the early postoperative period when this is
most desirable. Nonvalved implants require some form of ligature to control
flow until encapsulation has occurred or require a staged implantation in which
the plate is placed primarily on the sclera and the tube is inserted into the
anterior chamber approximately 6 weeks later during a second procedure.
The indications for performing implantation of an aqueous shunt are varied. Patients usually have elevated IOP despite maximum medical therapy and laser therapy and either have failed previous filtration surgery or have anatomic factors that limit the potential for successful filtration surgery. Aqueous shunts have been used in all types of glaucoma and have indications for primary insertion in patients with neovascular or other inflammatory glaucomas where the intense inflammatory nature of the disease most likely would cause irreparable scarring of a sclerostomy and scleral flap.129-134
Information about the design and flow characteristics of each implant is available elsewhere. Our preferred implant is the Baerveldt 350 mm2 implant. Many of the components of the surgical technique are identical among implants and vary only in the need to place some implants beneath rectus muscles and methods of restricting flow through the tube in the early postoperative period.
The first part of the procedure is the creation of a fornix-based conjunctival flap (Slide 13). Limbus-based flaps should be avoided as they may lead to late dehiscence and erosion.135 A relaxing incision at one side of the peritomy enhances surgical exposure. The conjunctiva is then undermined using blunt dissection, and a scleral pocket is created between the superior and lateral rectus muscles. A muscle hook then engages each muscle in succession to identify their insertions. The device is then placed on the surgical field and the tube is irrigated with balanced salt solution to ensure patency and to prime the valve on restrictive implants. In a nonrestricted device, such as the Baerveldt, a 7-0 or 8-0 polyglactin ligature is placed around the tube near its base and tied tightly with needle holders. The tube should then be irrigated again to be certain that there is no flow through the tube. An absorbable suture should be used because this will dissolve in 4 to 6 weeks, after encapsulation has occurred. Alternatively, laser suture lysis or releasable suture techniques can be used if earlier flow is required.136-138 Once the flow has been completely restricted, the plate is positioned between the sclera and Tenon's capsule and between the two rectus muscles. This is accomplished by pushing the plate posteriorly until it lies behind the muscle insertions, about 10 mm from the limbus. This process is facilitated by using the muscle hook to first identify the superior rectus insertion, placing the plate behind it, and then identifying the lateral rectus insertion. The implant is then attached to the sclera with two nonabsorbable nylon sutures placed through anchoring eyelets on the device. The drainage tube should then be positioned over the limbus at the proposed site of entry into the anterior chamber. Scissors should be used to cut the tube to a length that will allow it to extend for 2 mm to 3 mm into the anterior chamber without obscuring the visual axis. The tube should be cut with a bevel-up configuration that will limit the possibility of tube blockage from iris tissue or vitreous. A paracentesis incision is then created temporally to allow for anterior chamber access. If vitreous is present, a thorough automated anterior vitrectomy should be performed through the paracentesis prior to placement of the tube.
A 23-gauge needle is then used to create the tube entry site. In pseudophakic or aphakic patients, the anterior chamber is entered approximately 0.5 mm to 0.75 mm posterior to the limbus with the incision made at an oblique angle, the needle being parallel to the iris plane. In phakic patients, the incision is made 0.5 mm posterior to the limbus with the needle angled a slightly flatter plane to avoid injury to the lens. The plane of the incision should be sufficient to keep the tube positioned close to the iris and away from the corneal endothelium. The tube is then placed through the entry track and into the anterior chamber. If the tube is too long, it can be removed, trimmed, and reintroduced. It is better to have a tube that is slightly long than one that is too short. Tube movement can be minimized by gently securing it to the eye wall with a nonabsorbable 10-0 nylon suture placed beneath the tube 4 mm or 5 mm from the limbus. The knot should be tied without creating tension on the tube and is then buried to avoid conjunctival erosion.
The tube should be covered with a connective tissue graft135,139,140 (processed pericardium, sclera, dura) that measures approximately 5 mm x 5 mm. This graft should cover the tube entry site and helps prevent erosion of the tube through the conjunctiva. The graft usually is secured to the sclera with 8-0 absorbable sutures. The conjunctiva is closed with multiple absorbable sutures as necessary. The relaxing incision should be closed with a running absorbable suture. Typical subconjunctival and topical medications are then applied.
Modifications of this procedure relate to methods of restricting flow through the tube136,138,141-145 and to the position of tube insertion. The tube can be placed into the pars plana if a pars plana vitrectomy is planned or has been previously performed.146-151 This position limits the potential risk to the cornea from tube migration or anterior entry. Furthermore, a two-stage implantation technique can be used for nonrestrictive implants to avoid excessive flow and hypotony when immediate pressure reduction is not essential. In this situation, the plate is attached to the eye in the usual fashion but no ligature is placed around the tube. Instead, the tube is placed behind the muscle insertions and secured to the eye wall with nonabsorbable sutures to prevent its anterior migration. Encapsulation is allowed to occur for 4 to 6 weeks and a second procedure is then performed, which locates the tube and places it within the anterior or posterior segment as previously discussed. Flow through the tube is established immediately and, because encapsulation already has occurred, there is little chance for hypotony. This technique is advantageous for patients who are predisposed to the development of choroidal hemorrhage or patients who have flat anterior chambers.
Aqueous shunt devices greatly expand the surgical options for the treatment of glaucoma. It is hoped that modifications to this technology will lead to the development of a device with prolonged efficacy and low potential for hypotony.
Antifibrosis Therapy
The major cause of glaucoma filtration surgery failure is external scarring of the conjunctival bleb.152,153 The use of antifibrosis agents both during and after the operative procedure has greatly increased the success of this procedure.154-175 These agents are applied with the intent of limiting fibroblast proliferation at the site of the surgical fistula in eyes that are presumed to be at a higher risk for failure. Risk factors for increased scarring include younger age, black race, previous incisional surgery, conjunctival scarring, active inflammation, eyes with neovascular or uveitic glaucoma, and eyes with a long history of chronic topical medication usage. The two agents commonly used in current filtration surgery are 5-fluorouracil (5-FU) and mitomycin-C (MMC). The use of these medications has increased the success of filtration surgery, increased the level of IOP reduction, and decreased the need for additional postoperative pressure lowering therapy.
5-FU
5-FU works by selectively interfering
with the synthesis phase (S phase) of the cell cycle. This agent is converted
into a nucleotide analogue (5-fluoro-2-deoxyuridylate monophosphate), which
competitively inhibits an enzyme involved in DNA synthesis. Abnormal protein
products are produced within the cell, leading to death.176,177 All
actively dividing cells that come into contact with this agent are affected.
Numerous studies have shown a positive effect of 5-FU on success of filtration
surgery. The initial method of application of this chemotherapy was to
administer frequent subconjunctival injections in the immediate postoperative
period consisting of 5 mg of 5-FU per injection for a cumulative dose of
approximately 100 mg.170-172 The occurrence of significant side
effects including severe corneal epitheliopathy, however, led to many patients
receiving a lower amount of medication. 5-FU can also be administered
intraoperatively with a sponge application161,178,179 and/or in the
postoperative period. When administering 5-FU in the operating room, the
technique involves preparation of the scleral bed and outlining of the scleral
flap. A cellulose sponge is cut to create a rectangular piece of material
approximately 3 mm x 2 mm. The sponge is placed in undiluted 5-FU (50 mg/mL)
and then directly onto bare sclera. Tenon's capsule and conjunctiva should
cover the sponge for 5 minutes. The sponge is then removed from the eye and
discarded as chemotherapy by trained operating room staff. Copious irrigation
of the sclera, conjunctiva, and cornea is performed and instruments are rinsed
thoroughly. If the anterior chamber is inadvertently entered during creation of
the scleral flap, antifibrotic agents should be administered with care as there
is severe toxicity associated with intraocular administration of these
agents.180-183 In addition, if an unusually thin scleral flap is
created, adjunctive antifibrosis may not be indicated because excessive leakage
can occur. Once the surgery has been successfully completed, many surgeons
administer additional injections of 5-FU subconjunctivally in the immediate
postoperative period. The decision to administer these injections is based on
the appearance of the bleb and the level of IOP reduction desired. The
cumulative dose should be titrated to the level of corneal toxicity. Finally,
there is no consensus with regard to the best location to give these
subconjunctival injections. Many surgeons place them directly adjacent to the
bleb in the hope of exerting a more local effect, whereas others believe that
because the subconjunctival space is continuous, the injection can be given
anywhere and still have an effect at the site of filtration. Those who give the
injections inferiorly, away from the bleb, feel that there is less corneal
toxicity from leakage and less chance of inadvertent injection into the bleb
with subsequent intraocular spread. We routinely irrigate the eye with sterile
eye wash after any injection to lessen the chance of topical toxicity. The
procedure for injection is identical regardless of location and a 30-gauge
needle on a tuberculin syringe is placed at least 1 mm to 2 mm under the
conjunctiva before injection to lessen the likelihood of leakage. Five
milligrams can be administered per injection.
MMC
MMC is an antibiotic isolated from the
bacteria Streptomyces caespitosus176 and has been found to have
antitumor activity. It is a cell cycle nonspecific alkylating agent, which
interrupts DNA synthesis after short exposure to low concentrations of
medication.184-186 Many studies have shown a significant increase in
the success rate of filtration surgery when MMC is applied intraoperatively via
sponge application.187-191 The efficacy of this medication appears
to be greater than that of 5-FU154,155 but there also is an increase
in both the frequency and magnitude of complications. MMC is applied in the
same manner as sponge 5-FU. Various concentrations have been used, ranging from
0.2 mg/mL to 0.5 mg/mL and have been applied from 30 seconds to 5
minutes.189,191-202 We have had good results with 0.5 mg/mL applied
for 3 minutes in most patients. These parameters, however, should be titrated
based on the patient risk factors for surgical failure and on the status of the
conjunctiva. No postoperative injections are required because a single topical
application of MMC has been shown to have a continued anti-fibroblastic
response.
Among the most common complications associated with the use of adjunctive antifibrosis are corneal toxicity from 5-FU170,172,203,204 and hypotony with both agents.152,198,205-209 Both of these agents are designed to limit the fibroblastic response at the filtration site. Therefore, they also inhibit wound healing of the conjunctiva. Delayed wound closure can lead to prolonged hypotony and/or anterior chamber shallowing. In addition, hypotony maculopathy, defined as extremely low IOP, choroidal folds, decreased visual acuity, and disruption of the retinal pigment epithelium, can occur.208,210-215 This condition also can occur without wound leakage when excessive filtration is present. Finally, there is an increase in the incidence of late bleb-related infections when adjunctive 5-FU and MMC are used.199,216-222 Such infections are believed to be related to the bleb characteristics that develop in these eyes.193,223,224 The filtration blebs are usually thin, avascular, and cystic, and are prone to late leakage, which can predispose to infection.47,218,225-227 The potential for early and late complications associated with the use of these medications should be weighed against the desired surgical outcome and the need for enhanced IOP reduction in certain patients.
Complications of Filtering Surgery
Complications of filtering surgery may occur during surgery or in the early or late postoperative period.
Intraoperative Complications
Both the local and
systemic risks of anesthesia during glaucoma surgery have been discussed
previously and will not be reiterated here.
Conjunctiva
The first tissue to be handled during
glaucoma surgery is the conjunctiva. Careful handling of the conjunctiva is
critical for both success of the procedure and prevention of devastating
complications. Conjunctival leakage in the early postoperative period may lead
to hypotony, overfiltration, shallow anterior chamber, and failure to form a
bleb. When the leak finally seals, the conjunctiva may be scarred, thereby
increasing the likelihood of filtration failure. For these reasons,
intraoperative detection of conjunctival leakage is critical to maintaining
bleb function and enhancing bleb formation.
One of the easiest and often overlooked methods of eliminating conjunctival injury is to avoid the use of toothed forceps. During dissection, the conjunctiva should be manipulated with nontoothed forceps or surgical sponges to avoid accidental buttonhole injury. Scarred conjunctiva should be handled with particular care because adhesions may connect the conjunctiva to Tenon's capsule or episclera, increasing the possibility of inadvertent conjunctival perforation during blunt dissection. Lysis of adhesions should be done under direct observation of the external surface of the conjunctiva to avoid accidental incorporation of conjunctiva and subsequent buttonhole formation. At the conclusion of surgery, fluorescein dye should be applied to the conjunctival surface and the bleb expanded by anterior chamber irrigation to aid in the detection of previously unrecognized buttonhole defects or wound leaks.
A buttonhole detected intraoperatively should be closed in the operating room. The location of the conjunctival tear determines the method of repair. If a large buttonhole is noted during the early stages of a filtration operation, it is best to select a new surgical site. If it occurs at a later stage, tension at the wound edge must be relieved prior to closure to avoid excessive tension at the buttonhole. If the buttonhole is located in the center of the conjunctival flap or more posteriorly, a "purse string" ligature with 10-0 or 11-0 nylon can be attempted, either internally on the under surface of the conjunctiva or externally. A tapered atraumatic needle should be used to avoid creating a larger conjunctival defect, and Tenon's capsule should be incorporated into the repair if this tissue is present to provide added support. The most common location for a buttonhole is near the limbus, where it may either be oversewn with adjacent conjunctiva, sutured directly to the cornea or sclera, closed as a "purse string," or sealed with the application of a tissue patch.228 If the buttonhole is small at this location, creating a conjunctival peritomy and excising the buttonhole can repair it. The corneal epithelium in this area should be removed and the conjunctiva sutured to the cornea with mattress sutures to facilitate adhesion. We prefer 9-0 polyglactin or 10-0 monofilament nylon on a cardiovascular needle. Small buttonholes near the posterior edge of a limbus-based flap can also be removed in this manner as long as there is enough tissue to allow the wound to be closed without excessive tension. If a violation of the conjunctiva occurs prior to placement of adjunctive antifibrosis agents, consideration should be given to avoiding their use.
Scleral Flap
Most complications related to the
scleral flap arise from inadequate thickness. Thin flaps may macerate, dehisce,
or avulse during dissection, manipulation, or suture placement. If a hole is
created in the scleral flap overlying the sclerostomy, excessive leakage can
occur with resultant hypotony. Suturing with 10-0 nylon and attempting to
incorporate a Tenon's plug if possible can repair this hole.229 If
necessary, a donor scleral or dura mater graft can be used to create a new
scleral flap, which is sutured through the cornea to recreate a hinged flap. If
a tear is created in the flap near its insertion, tight closure of the flap
with nylon sutures prevents excessive flow. If the scleral flap is too thick,
the anterior chamber can be entered prematurely at a posterior location. If
this is the case, excessive outflow may occur due to an inability to adequately
close the flap posteriorly. Injury to the ciliary body also can occur.
Anterior Chamber
Every attempt should be made to
avoid excessive shallowing of the anterior chamber during surgery. Shallowing
of the chamber can lead to endothelial damage from inadvertent lens-cornea
touch. Preplaced scleral flap sutures may facilitate wound closure and are
particularly useful in aphakic, pseudophakic, vitrectomized, or highly myopic
eyes. Some surgeons have advocated the use of intraoperative viscoelastic
agents during routine filtering surgery. Potential advantages include
maintenance of anterior chamber depth during surgery, tamponade of bleeding,
and, in theory, decreased incidence of postoperative shallowing of the anterior
chamber.230-233 Several studies, however, have shown no benefit of
these agents in maintaining anterior chamber depth and preventing hypotony in
the early postoperative period.234,235 In addition, they can cause
significant elevation of IOP or can tamponade the surgical wound, thereby
masking a previously undetected leak.236
Hyphema
Intraoperative anterior chamber hemorrhage
most commonly occurs at the time of iridectomy from cut radial iris vessels or
from a traumatized greater arterial circle within the ciliary body. Bleeding is
best treated with observation, as most iris root/ciliary body bleeding
spontaneously stops within minutes. The scleral flap should be held open while
the pulsatile bleeding continues to allow the blood to exit the eye. This
technique and gentle irrigation keep the anterior chamber from filling with
blood. It is important that the scleral flap not be sutured until all bleeding
has stopped to prevent postoperative blockage of the internal ostium by the
clotted blood. Persistent bleeding also may be treated with viscoelastic
tamponade. Cautery is ill-advised, as it may lead to cataract formation in
phakic patients or vitreous loss from inadvertent involvement of the hyaloid
face through the iridectomy. It is unnecessary to vigorously irrigate the
anterior chamber to remove small amounts of blood as most hyphemas clear
spontaneously without adverse sequelae.
Vitreous Loss
Vitreous loss is rare during
glaucoma filtration surgery in phakic eyes but can complicate combined cataract
extraction and trabeculectomy. In addition, vitreous may be present within the
anterior chamber of aphakic and pseudophakic patients. Vitreous in the anterior
chamber presents a problem because it can plug the sclerostomy and lead to
surgical failure. Furthermore, vitreous can incarcerate within the scleral flap
leading to delayed wound closure and, possibly, hypotony. A complete anterior
vitrectomy should be performed in any eye where vitreous is present and
threatens the success of filtration surgery. Occasionally, viscoelastics also
can be used intraoperatively to tamponade the movement of vitreous during the
procedure, especially if the vitreous is present behind the iris plane.
Viscoelastic can be used to move the vitreous posteriorly so that an iridectomy
can be performed.
Choroidal Hemorrhage
Suprachoroidal
hemorrhage can occur intraoperatively or postoperatively.237-239
Patients often experience sudden, severe pain even with adequate local
anesthesia at the time of surgery. During surgery, the anterior chamber
shallows, the IOP rises, and a dark posterior segment mass may become visible
through the pupil. Intraoperative, expulsive choroidal hemorrhage is rare in
phakic eyes undergoing trabeculectomy. Delayed choroidal hemorrhage occurs more
commonly and is associated with postoperative hypotony.240-243
Several risk factors have been associated with this condition and include
advanced age, systemic vascular disease, aphakia, high myopia, previous
vitrectomy, and elevated preoperative pressure.241,244,245 The
occasional bucking and straining associated with extubation after general
anesthesia and postoperative coughing or vomiting are also risk
factors.246,247 Delayed choroidal hemorrhage often occurs in the
situation of prolonged hypotony and choroidal effusion. Patients often describe
a history of performing physical activities that are too strenuous for their
recommended postoperative activity restrictions.
Choroidal hemorrhage usually occurs intraoperatively at a time of relative hypotony. When this condition is identified, the eye should be closed immediately.248 The anterior chamber should be reformed with balanced salt solution, viscoelastic, or air. Often, posterior sclerotomies are performed to drain the choroidal hemorrhage when there is an inability to limit the spread of the bleeding within the posterior segment. Once the eye has been closed, IV acetazolamide and mannitol may be used to lower the IOP and stabilize the eye. The prognosis for recovery of vision remains fair as long as the eye can be closed without loss of uvea or retina. Later, drainage of the hemorrhage may be necessary. The most important factor related to a positive outcome is early recognition and immediate wound closure.
Delayed postoperative choroidal hemorrhage is more common than intraoperative choroidal hemorrhage following glaucoma surgery. Acute onset of severe pain and decreased vision are the usual presenting symptoms. Patients should not be routinely placed on postoperative narcotics because severe pain often means either a postoperative choroidal hemorrhage or markedly elevated IOP with corneal edema, both of which warrant immediate examination. Limited choroidal hemorrhages without retinal detachment or vitreous hemorrhage typically resolve and are best treated with observation.247,249 In cases in which there is severe, intractable pain, retinal detachment, hypotony, or vitreous hemorrhage, surgical drainage often is performed.250,251 Concurrent retinal therapy is performed at the same time, if necessary. It is helpful to delay the drainage for at least 7 to 14 days, if possible, because liquefaction of the clot during this period facilitates its removal.239,252
Avoiding prolonged hypotony is the best way to prevent this devastating complication both in the operating room and during the postoperative period.241,243,247 We routinely prescribe stool softeners to all patients undergoing filtration surgery and educate patients regarding the avoidance of strenuous activities that involve bending or lifting.243 Postoperative nausea and vomiting should be addressed.
Early Postoperative Complications
Early
postoperative complications not already discussed are related specifically to
the function of the trabeculectomy or operative technique. Many of these
complications are related to pressure control within the eye and will be
divided into those conditions associated with elevated IOP and those associated
with decreased IOP.
Elevated IOP
Early undetected rises in pressure
after trabeculectomy occur with surprising frequency.236 In susceptible eyes
with advanced visual field loss, further visual field loss or loss of central
fixation may occur and can account for the so-called snuff phenomenon described
following filtration surgery. There are many potential causes of elevated
pressure. In the presence of a deep anterior chamber, the most common cause of
elevated pressure is tight scleral flap sutures with inadequate filtration.253
Also, blockage of the internal ostium by iris tissue, incompletely excised
Descemet's membrane, blood clot, fibrin, vitreous, lens capsule, or ciliary
processes may also account for this situation. Retained viscoelastic material
can also cause significant elevation of the IOP.
Management of elevated IOP depends on the specific etiology. Scleral flap suture release is possible with the aid of the argon laser or releasable suture techniques. The advantage of laser suture lysis is that the suture ends remain buried beneath the conjunctiva, whereas releasable sutures remain exteriorized and may protrude for an extended period of time if they do not need to be released. The disadvantage, however, is that extensive subconjunctival hemorrhage or thickened Tenon's capsule may prevent laser suture lysis in some eyes. Suture lysis should be completed within 7 to 10 days for trabeculectomy without antiscarring medications, within 14 days for 5-FU trabeculectomy, and within 1 month for MMC trabeculectomy. We routinely make a postoperative notation as to flap suture tension and lyse the tightest suture first. In this manner, a desired reduction in IOP can be achieved while the remaining scleral flap sutures remain, providing support that decreases the likelihood of prolonged hypotony. If the IOP is elevated in the immediate postoperative period (i.e., fewer than 5 days), we recommend conservative management with topical and systemic antiglaucoma medications, gentle bleb massage if appropriate, or paracentesis. Suture lysis should be avoided in the first 72 hours to reduce the risk of hypotony. In addition, only one suture should be cut at a time.
Laser suture lysis should be performed with as little conjunctival manipulation and laser energy as possible. Care must be taken to avoid a potential conjunctival burn or buttonhole injury. This may be accomplished by defocusing the beam posteriorly. In the presence of a subconjunctival hemorrhage, a diode or krypton laser should be used rather than the argon laser, because argon energy is absorbed by the blood and can result in a conjunctival burn or buttonhole. Settings of 0.05 seconds, a 50-µm spot size, and 200 mW to 400 mW power usually are sufficient. Cautious digital massage or pressure to the edge of the scleral flap following suture lysis often helps to elevate the bleb if it does not do so spontaneously. If the bleb remains flat even with massage, it is a sign of impending bleb failure.
Gonioscopy is required to identify a blockage of the internal ostium and should be performed without injury to the conjunctiva. The etiology of the blockage dictates the course of therapy, which ranges from observation of retained viscoelastic to incisional surgery for removal of lens fragments. The Nd:YAG laser has been effective in cases in which surgery may have been indicated.254-257
The presence of a shallow anterior chamber associated with elevated IOP usually indicates the development of malignant glaucoma. The differential diagnosis includes pupillary block, choroidal hemorrhage, annular choroidal detachment with anterior rotation of the ciliary body causing angle closure, and malignant glaucoma. Posterior pooling of aqueous either within or behind the vitreous causes forward movement of the lens-iris or hyaloid-iris diaphragm, resulting in a flat anterior chamber with an elevated pressure. Medical treatment of aqueous misdirection is successful in approximately 50% of cases and consists of intense cycloplegia, aqueous suppression, and systemic administration of a hyperosmotic and a carbonic anhydrase inhibitor, if necessary.258 Therapy may also include argon laser treatment of visible ciliary processes and Nd:YAG anterior hyaloidectomy or posterior capsulotomy in aphakic and pseudophakic eyes.259,260 Surgical therapy is necessary if these medical and laser techniques are ineffective and usually consists of pars plana vitrectomy and lensectomy with rupture of the vitreous face in phakic eyes, and a limbal vitrectomy in aphakic eyes.258,261-263
Decreased IOP
Low IOP in the early postoperative
period may be associated with a shallow anterior chamber. In this scenario, the
etiology may be overfiltration, ciliochoroidal detachment with reduced aqueous
production, a cyclodialysis cleft, or a wound leak.35,264-267
Overfiltration usually is caused by loose scleral flap sutures and is less common today with the trend toward tighter scleral flap sutures and early laser suture lysis. If an exuberant bleb has formed after guarded filtration surgery, the best management usually is external compression with a contact lens that compresses the bleb and/or scleral support from a Simmons shell or symblepharon ring. The use of these devices must be weighed against the potential for bleb failure. Consideration can be given to decreasing the level of postoperative anti-inflammatory medication in an attempt to promote wound healing, which may increase the resistance to flow, but this too has potential for increasing the likelihood of long-term failure of the procedure. External compression sutures can also be used. This technique involves a nylon suture placed over a portion of the bleb in an attempt to cause localized scarring and an overall decrease in the effective size of the filtering bleb.
A wound leak is one of the most common causes of hypotony in the early postoperative period. Leakage may be from a conjunctival flap perforation not recognized at the time of surgery, an area of inadvertent, postcautery conjunctival necrosis, a wound dehiscence, or a traumatized, thin filtration bleb.268-270 Although the site of leakage often can be determined with a Seidel test,271,272 gentle external pressure on the globe may be required to increase flow sufficiently to demonstrate a hole during times of decreased aqueous production. Early wound dehiscence when limbus-based conjunctival flaps are used and retraction of the flap in fornix-based cases are the most serious wound-related complications and generally require immediate surgical repair, particularly if the edge of the scleral flap becomes exposed. The administration of aqueous suppressants can enhance the closure of some leaks by decreasing flow across the leak.273 Nevertheless, a further reduction in IOP can occur, which may cause an increased shallowing of the anterior chamber. Definitive therapy for all wound leaks is surgical closure. This procedure is often performed in a minor surgical suite or even at the slit lamp. A tapered, noncutting cardiovascular needle should be used at all times, if possible, to avoid additional leakage at the suture tracks.274 With thin, cystic blebs, a large diameter soft contact lens, symblepharon ring, or a Simmons shell often is successful in mechanically sealing the wound leak and reforming the anterior chamber.275,276 Tissue adhesive also has been used. 277
Choroidal effusions can occur in any situation in which there is decreased IOP.278 This process further enhances hypotony by decreasing aqueous production due to abnormal positioning of the ciliary body. Hypotony leads to transudation of fluid into the potential space between the sclera and uveal tissues.264,279 Development of an effusion in the absence of hypotony typically occurs in conjunction with inflammation because of protein accumulation in the ciliochoroidal space. When hypotony is present, it often is difficult to ascertain whether the hypotony caused the ciliochoroidal detachment, or vice versa. In cases in which choroidal effusions are isolated and not found in association with wound leaks or overfiltration, the detachment usually is transient and lasts for 10 to 14 days. In these cases, the only treatment required is frequent topical and possibly systemic steroid administration. Most cases of effusion resolve spontaneously and surgical drainage usually is indicated only for chronic effusions and for cases of prolonged "kissing choroidals" in which retinal apposition may lead to retinal tears upon separation. In the presence of flat anterior chamber with lens-cornea touch, reformation of the chamber with viscoelastic280 or air often causes some resolution of the effusion.
Late Complications
Leaks
Although leaks that develop months to years
after filtration surgery may be accompanied by an increased risk of
endophthalmitis and hypotony maculopathy, they also may continue for prolonged
periods without any adverse sequelae.220,281,282 The decision to
treat late leaks depends on the clinical situation. If there is compromise of
the anterior chamber or complications of prolonged hypotony, then treatment
should be initiated. Treatment options include patching, bandage contact
lenses, focal cautery, laser photocoagulation, cryotherapy, tamponade shells,
aqueous suppressants, tissue patches, cyanoacrylate, intrableb injection of
autologous blood, and surgical revision.283-294
Hypotony
Chronic hypotony occurs more frequently
when full-thickness procedures or trabeculectomy with 5-FU or MMC are used than
in guarded procedures without antifibrosis agents. Although IOPs of 4 mm Hg to
10 mm Hg have not been shown to increase the incidence of visual
compromise,92 IOPs of less than 4 mm Hg more commonly have been
associated with the development of vision threatening
maculopathy.212,295 The fundus changes associated with this
condition include disc edema, choroidal and retinal folds, and retinal vascular
engorgement. Often, there is a failure to return to baseline visual acuity even
with complete resolution of the maculopathy. Treatment for this condition
revolves around treatment of the etiology of the hypotony.296-298
Cataract
Cataract progression has been reported
after some filtration surgeries.35,42,299-301 The incidence of
progression has been reported to be from 2% to 53%. Such progression has been
associated with multiple factors including increased postoperative steroid
usage, hypotony, and flat anterior chamber.32 There are no clear
data linking the actual procedure to cataract progression, and there are a
variety of associated factors that have not been thoroughly analyzed (i.e.,
miotic usage and degree of preexisting cataract).
Filtration Failure
Elevated IOP after
filtration surgery with poor bleb function is the most common complication of
filtering surgery. Risk factors associated with increased surgical failure
include prolonged preoperative topical antiglaucoma medication
usage,18-21 neovascular glaucoma,31,302 black
race,26,39,50,303 young age,44,46,47
aphakia,304-306 previous failed filtering surgery,307,308
previous cataract surgery,43 and uveitis.29,30 The
failure may be due to multiple factors ranging from blockage of the internal or
external ostium to bleb encapsulation. Early in the postoperative period, signs
of potential problems preventing adequate filtration may develop. Early
recognition of the signs, symptoms, and patterns of filtration failure allows
for timely intervention to encourage filtration. Such recognition is
particularly important during the first 2 weeks after surgery when the healing
process is most active.
The appearance of the bleb is the most important factor in determining possible bleb failure.309 Injection and vascularization of the bleb indicate the presence of inflammation, usually occur before an elevation of the IOP, and are poor prognostic signs.310 In addition, decreased height of the bleb indicating poor flow and progressive loculation may indicate the development of bleb encapsulation. Although gonioscopy frequently can help to identify a blockage of the internal ostium, blockage of the external ostium often is a diagnosis of exclusion when no other signs of failure are present. If digital compression of the globe fails to elevate the bleb and the internal ostium is free of obstruction, the obstruction typically is at the level of the external ostium. Transient bleb formation and a lowering of the IOP with compression suggest the presence of tight scleral flap sutures or loculation. 311
Once the cause of the failure has been isolated, appropriate treatment may prolong the life of a failing filter. Because repeat filtration surgery often is unrewarding, it is best to maximize the effect of the initial surgery with all appropriate interventions.
Management of the failing filter requires therapy directed toward the level of blockage to aqueous flow and toward blocking the wound healing response to both the initial surgery and the planned intervention. For example, increased scarring of the bleb can be treated with intense anti-inflammatory medication and possibly with adjunctive 5-FU injections. Elevation of the conjunctiva with viscoelastic or balanced salt solution to reduce apposition of this tissue to the sclera also may decrease blockage at the level of the external ostium. Internal blockage of the ostium may be treated by laser revision or automated trephination, which effectively converts the procedure to a full-thickness trabeculectomy.312,313 Bleb encapsulation, or Tenon's cyst formation, develops in approximately 10% to 28% of eyes undergoing trabeculectomy.314-319 The encapsulation process consists of fibroblastic overgrowth that results in a tense, opalescent bleb with a thick wall in direct communication with the anterior chamber. There usually is loculation, thickening of the subconjunctival connective tissue, and elevated IOP. There is a spectrum of appearance ranging from incomplete loculation with mild hyperemia to complete encapsulation. The dome-like cyst is firm and often has mobile conjunctiva overlying it. The key to successful management is patience. In most cases, the pressure decreases within 2 to 4 months with the use of aqueous suppressants.320 Extended use of aqueous suppressant following filtering surgery, however, may limit the extent of bleb formation by decreasing flow through the fistula. After resolution, the antiglaucoma therapy may be tapered.
Many encapsulated blebs, particularly those that are only partially loculated, may resolve spontaneously or respond to intensive topical steroid therapy or digital compression. If resolution of the encapsulated bleb does not occur and a cyst is present, the cyst can be punctured with a needle.316,321-323 Bleb needling allows the surgeon to create an opening in the wall of an encapsulated bleb or to raise a flattened bleb at the slit lamp via subconjunctival manipulation with a small gauge needle. The technique involves elevation of the conjunctiva off the surface of the globe with balanced salt solution or anesthetic using a 30-gauge needle. The underlying episcleral/Tenon's capsule scarring then is incised with the needle. If this technique does not succeed in restoring filtration, the edge of the scleral flap may be elevated. Entry into the anterior chamber also can be performed in pseudophakic or aphakic patients but this action carries with it the increased risks of hyphema and infection. This procedure can be combined with a pre-needling injection of MMC or with a full post-needling course of 5-FU injections.321,323-326 Many times, needle revision allows the patient to be spared another trip to the operating room.309,327,328
Bleb-Related Infection
Early postoperative
endophthalmitis is caused by penetration of organisms at the time of surgery
and is not related to the presence of a filtering bleb. Nevertheless,
bleb-related ocular infection can occur months to years after filtration
surgery and has been reported to range between 0.2% and
9.6%.216,220,282 The incidence of infection is greatest with
full-thickness procedures.329 With the increased use of antifibrosis
agents producing blebs similar to those found after full-thickness procedures,
however, the late bleb-related endophthalmitis rate once again is increasing.
The route of infection is believed to involve migration of bacteria through the
thin and cystic bleb walls of filters using 5-FU and MMC. The potential for
infection is greater in eyes with positive Seidel's test and in eyes that have
had filtration surgery from below. Additional associations include diabetes
mellitus, malnutrition, blepharitis, and a compromised immune system.
The clinical presentation of endophthalmitis usually is one of sudden onset of pain and redness, which often is localized to the filtration area, and is associated with photophobia and decreased visual acuity. Examination reveals bleb purulence and intraocular inflammation that may involve the posterior segment. When ocular involvement is limited to the anterior segment, treatment with topical, periocular, and systemic antibiotics is possible. If the vitreous is involved, more aggressive therapy is necessary and usually requires vitreous tap or pars plana vitrectomy with intravitreal antibiotics and steroids.
Surface cultures often do not yield the offending agent and may yield results different from intraocular cultures.226 Although a wide range of gram-positive and gram-negative organisms have been reported, staphylococcal and streptococcal species are the most common.
Patients should be instructed to immediately report any redness, pain, discharge, or decreased vision and should be treated intensively to avoid loss of vision, because good visual outcome depends upon early treatment. Although chronic antibiotic therapy has never been shown to effectively prevent the onset of bleb-related endophthalmitis, consideration of such therapy in eyes at high risk for infection seems reasonable.47 This includes eyes with thin, avascular, leaking blebs, or blebs located in the inferior quadrants.216,226 Antibiotics should be alternated periodically to minimize the development of drug-resistant organisms.
Complications of Aqueous Shunts
Aqueous
shunts are associated with the same operative and postoperative complications
as trabeculectomy including hyphema, pupillary block, aqueous misdirection,
choroidal hemorrhage, and infection.330-337 Hypotony is usually
related to leakage around the tube entry site or failure of a restrictive valve
to regulate the IOP.123,331,338 When leakage around the tube is
present, it usually resolves spontaneously after 10 to 14 days. Choroidal
hemorrhage occurs in up to 8% of eyes that receive glaucoma
implants.339,340
Some complications, however, are unique to tube shunt implantation. Epithelial ingrowth can occur if the anterior chamber entry site is in the cornea rather than posterior.341,342 This is a difficult problem to battle and one that should be avoided at all costs. In addition, improper tube placement can cause injury to the cornea, iris, and lens in phakic patients. Elevated IOP may occur from obstruction of the tube opening from blood, vitreous, fibrin, and even iris tissue. Various laser techniques have been used to clear visible blockages343-345 and flushing the tube with a cannula may be necessary when no obvious obstruction is visible.346 Elevated IOP also can be related to encapsulation around the plate. The process is similar to that found with Tenon's cyst formation after trabeculectomy347 and often responds to needling procedures.348 Finally, migration of the tube against the cornea leading to corneal edema and bullous keratopathy from endothelial cell dysfunction can occur. In rare cases, the tube can migrate completely out of the eye. Both of these situations require prompt repositioning of the tube, if possible, or removal of the implant.
Finally, a unique complication of tube shunt implantation is transient or permanent diplopia.349-357 Many patients have transient diplopia in the immediate postoperative period related to periocular edema and swelling. This is similar to the diplopia seen after scleral buckling. Permanent, restrictive diplopia is a more significant problem and may occur from a large bleb causing compression against the orbital contents with decreased motility353,358 or scarring between the plate and either the recti or oblique muscles. Strabismus appears to be more common with the Baerveldt implant350 and is related to the placement of a significant portion of the plate under a vertical and horizontal rectus muscle. If diplopia is intractable and not responsive to conservative therapy with prisms, the risks and benefits of removal of the device should be discussed with the patient.
Postoperative Management of Filtration Surgery
Many of the postoperative recommendations and therapy strategies have already been discussed. A few general principles, however, will be reviewed. First, it is important to remember that patients who undergo trabeculectomy require frequent follow-up visits during the early postoperative period. Patients should be informed of this before their surgery so that appropriate preparation can be made. If there are significant complications, daily visits may be required for some time. In addition, patients should have severe restrictions placed upon their activity level. Valsalva maneuvers should be avoided. Anterior chamber shallowing also may occur with the presence of effusions in this circumstance. We routinely provide patients with stool softeners to be used during the early postoperative period, as well.
All patients who undergo intraocular surgery are placed on a regimen of topical antibiotics and anti-inflammatory medication. The same holds true for filtration surgery. The regimen of postoperative anti-inflammatory medication usually is more vigorous than with other surgeries because an effort also is being made to prevent healing at the filtration site in addition to decreasing intraocular inflammation. Most patients require prednisolone acetate 1% every 1 to 2 hours while awake for the first 3 or 4 weeks.359 This medication is tapered based on the patient's response and the use of additional therapy to control wound healing such as adjunctive antifibrosis injections. Antibiotics often are discontinued after the first 7 to 10 days unless there is a suspicion of any infectious process including active blepharitis. Cycloplegic agents usually are given to all phakic patients for control of pain and to lessen the likelihood and severity of any anterior chamber shallowing associated with hypotony, choroidal effusions, or aqueous misdirection. This medication also is tapered as the healing process continues.
Laser suture lysis, digital bleb compression, and needle revision have been discussed previously as methods of lowering the IOP and preserving bleb function. The appropriate timing and sequence of these events are based on a thorough knowledge of filtration surgery, the patient's diagnosis, and extensive surgical experience.
Glaucoma surgery is only the beginning of the process. Intensive therapy and intervention are required to preserve bleb function, and it often takes many months before stabilization is achieved. The role of the glaucoma surgeon is to perform the appropriate surgery and to provide comprehensive postoperative care to ensure the success of that procedure. He or she must possess knowledge of advanced techniques and must be able to identify and treat all of the possible intra- and postoperative complications. It is this knowledge that provides patients with the best chance for preservation of their visual function.
Note: Supported by a grant from the New York Glaucoma Research Institute, New York, NY.
References
- David R, Livingston DG, Luntz MH. Ocular hypertension - a
long-term follow-up of treated and untreated patients. Br J Ophthalmol.
1977;61:668.
- Walker WM. Ocular hypertension: Follow-up of 109 cases from
1963 to 1974. Trans Ophthalmol Soc UK. 1974;94:525.
- Gaasterland D, et al. Studies of aqueous humor dynamics in
man. VI. Effect of age upon parameters of intraocular pressure in normal human
eyes. Exp Eye Res. 1978;26:651.
- Chauhan BC, Drance SM, Douglas GR, et al. Visual field
damage in normal-tension and high-tension glaucoma. Am J Ophthalmol.
1989;108(6):636-42.
- Kass MA, Hart WMJ, Gordon M, et al. Risk factors favoring
the development of glaucomatous visual filed loss in ocular hypertension.
Surv Ophthalmol. 1980;25:155-162.
- Armaly MF. The visual field defect and ocular pressure
level in open-angle glaucoma. Invest Ophthalmol. 1969;8:105.
- Armaly MF. Ocular pressure and visual fields. A ten-year
follow-up study. Arch Ophthalmol. 1969;81:25.
- Mao LK, Stewart WC, Shields MB. Correlation between
intraocular pressure control and progressive glaucomatous damage in primary
open-angle glaucoma. Am J Ophthalmol. 1991;111:51-55.
- Quigley HA, Maumenee AE. Long-term follow-up of treated
open-angle glaucoma. Am J Ophthalmol. 1979;87:519.
- Stewart WC, Chorak RP, Hunt HH, et al. Factors associated
with visual loss in patients with advanced glaucomatous changes in the optic
nerve head. Am J Ophthalmol. 1993;116:176.
- MacKenzie W. A Practical Treatise on Diseases of the
Eye. London, England: Longman, Rees, Orm, Brown & Green; 1830.
- Kronfeld P. The rise of the filter operations. Surv
Ophthalmol. 1972;17:168.
- Spaeth GL. Guarded filtration procedure-not
trabeculectomy. Ophthalmic Surg. 1992;23:583.
- Sugar HS. Filtering operations: an historical review.
Glaucoma. 1981;3:85.
- Gutierrez P, Wilson MR, Johnson C, et al. Influence of
glaucomatous visual field loss on health-related quality of life. Arch
Ophthalmol. 1997;115(6):777-784.
- Shin DH. Trabeculectomy. Int Ophthalmol Clin.
1981;21:47.
- Smith RJ. Medical versus surgical therapy in glaucoma
simplex. Br J Ophthalmol. 1972;56(3):277-283.
- Broadway D, Grierson I, Hitchings R. Adverse effects of
topical antiglaucomatous medications on the conjunctiva. Br J
Ophthalmol. 1993;77:590-596.
- Broadway DC, Grierson I, O'Brien C, et al. Adverse effects
of topical antiglaucoma medication. II. The outcome of filtration surgery.
Arch Ophthalmol. 1994;112:1446-1454.
- Lavin MJ, Wormald RPL, Migdal CS, et al. The influence of
prior therapy on the success of trabeculectomy. Arch Ophthalmol.
1990;108:1543-1548.
- Sherwood MB, Grierson I, Millar L, et al. Long-term
morphologic effects of antiglaucoma drugs on the conjunctiva and Tenon's
capsule in glaucomatous patients. Ophthalmology.
1989;96:327-335.
- Jay JL. Earlier trabeculectomy. Trans Ophthalmol Soc
UK. 1983;103:35.
- Migdal C, Hitchings R. The role of early surgery for open
angle glaucoma. Ophthalmol Clin N Amer. 1991;4:853-861.
- Sherwood MB, Migdal CS, Hitchings RA. Filtration surgery as
the initial therapy for open-angle glaucoma. J Glaucoma.
1993;2:64-67.
- Sherwood MB, Migdal CS, Hitchings RA, et al. Initial
treatment of glaucoma: Surgery or medications. Surv Ophthalmol.
1993;37:293-305.
- Miller RD, Barber JC. Trabeculectomy in black patients.
Ophthalmic Surg. 1981;12:46-50.
- McMillan TA, et al. Histologic differences in the
conjunctiva of black and white glaucoma patients. Ophthalmic Surg.
1992;23:762-765.
- Freedman J, Shen E, Ahrens M. Trabeculectomy in a black
American glaucoma population. Br J Ophthalmol. 1976;60:573-574.
- Hoskins HD Jr , Hetherington J Jr , Shaffer RN. Surgical
management of the inflammatory glaucomas. Perspect Ophthalmol.
1977;1:173-181.
- Jampel HD, Jabs DA, Quigley HA. Trabeculectomy with
5-fluorouracil for adult inflammatory glaucoma. Am J Ophthalmol.
1990;109:168-173.
- Allen RC, Bellows AR, Hutchinson BT, et al. Filtration
surgery in the treatment of neovascular glaucoma. Ophthalmology.
1982;89:1181-1187.
- D'Ermo F, Bonomi L, Doro D. A critical analysis of the
long-term results of trabeculectomy. Am J Ophthalmol.
1979;88:829-835.
- Eltz H, Gloor B. Trabeculectomy in cases of angle-closure
glaucoma-successes and failures. Klin Monatsbl Augenheilkd.
1980;177:556.
- Jerndal T, Kriisa V. Results of trabeculectomy for
pseudoexfoliation glaucoma. Br J Ophthalmol. 1974;58:927.
- Mills K. Trabeculectomy: A retrospective long-term
follow-up of 444 cases. Br J Ophthalmol. 1981;65:790-795.
- Tornqvist G, Drolsum LK. Trabeculectomies. A long-term
study. Acta Ophthalmol. 1991;69(4):450-454.
- Vesti E. Filtering blebs: follow up of trabeculectomy.
Ophthalmic Surg. 1993;24:249-255.
- Watson PG, Barnett F. Effectiveness of trabeculectomy in
glaucoma. Am J Ophthalmol. 1975;79:831-845.
- Watson P, Grierson I. The place of trabeculectomy in the
treatment of glaucoma. Ophthalmology. 1981;88:175-196.
- Gilvarry AM, et al. The management of post-keratoplasty
glaucoma by trabeculectomy. Eye. 1983;3:713.
- Shirato S, Kitazawa Y, Mishima S. A critical analysis of
the trabeculectomy results by a prospective follow-up design. Jpn J
Ophthalmol. 1981;26:468.
- Jerndal T, Lundstrom M. 330 Trabeculectomies - a long time
study (3-5 1/2 years). Acta Ophthalmol. 1980;58:947.
- Gross RL, Feldman RM, Spaeth GL, et al. Surgical therapy of
chronic glaucoma in aphakia and pseudophakia. Ophthalmology.
1988;95:1195-1201.
- Gressel MG, Heuer DK, Parrish RK II. Trabeculectomy in
young patients. Ophthalmology. 1984;91:1242-1246.
- Levene RZ. Glaucoma filtering surgery: factors that
determine pressure control. Trans Am Ophthalmol Soc.
1984;82:282.
- Cadera W, Pachtman MA, Cantor LB, et al. Filtering surgery
in childhood glaucoma. Ophthalmic Surg. 1984;15:319-322.
- Lamping KA, Bellows AR, Hutchinson BT, et al. Long-term
evaluation of initial filtration surgery. Ophthalmology.
1986;93:91-101.
- Ridgeway AEA. Trabeculectomy: A follow-up study. Br J
Ophthalmol. 1974;58:680-686.
- Ridgeway AEA, Rubinstein K, Smith VH. Trabeculectomy: a
study of 86 cases. Br J Ophthalmol. 1972;56:511-516.
- Schwartz PL, Ackerman J, Beards J, et al. Further
experience with trabeculectomy. Ann Ophthalmol. 1976;8:207-217.
- Ellis EP, Esterdahl M. Echothiophate iodide therapy in
children: Effect upon blood cholinesterase levels. Arch Ophthalmol.
1967;77:598.
- Barash PG, Cullen BF, Stoelting RK. Handbook of Clinical
Anesthesia. Philadelphia, Pa: Lippincott; 1991.
- Krohne SG. Effect of topically applied 2% pilocarpine and
0. 25% demecarium bromide on blood-aqueous barrier permeability in dogs. Am
J Vet Res. 1994;55(12):1729-1733.
- Roberts CW. Intraocular miotics and postoperative
inflammation. J Cataract Refract Surg. 1993;19:731-734.
- Mori M, Araie M. Effect of apraclonidine on blood-aqueous
barrier permeability to plasma protein in man. Exp Eye Res.
1992;54:555-560.
- Bellan L. Preoperative testing for cataract surgery.
Can J Ophthalmol. 1994;29(3):111-114.
- Steinberg EP, Bass EB, Luthra R, et al. Variation in
ophthalmic testing before cataract surgery. Results of a national survey of
ophthalmologists [see comments]. Arch Ophthalmol.
1994;112(7):896-902.
- Bruce AB, McGoldrick KE, Oppenheimer P. Anesthesia for
Ophthalmology. Birmingham, Ala: Aesculapius; 1982.
- Dereklis DL, Bufidis TA, Tsiakiri EP, et al. Preoperative
ocular disinfection by the use of povidone-iodine 5%. Acta Ophthalmol.
1994;72(5):627-630.
- Speaker MG, et al. Role of external bacterial flora in the
pathogenesis of acute postoperative endophthalmitis. Ophthalmology.
1991;98:639.
- Denha RF, Wraight WJ. Local or general anaesthesia for
cataract surgery [letter; comment]. Anaesthesia.
1996;51(12):1191-1192.
- Barker JP, Vafidis GC, Hall GM. Postoperative morbidity
following cataract surgery. A comparison of local and general anaesthesia [see
comments]. Anaesthesia. 1996;51(5):435-437.
- Campbell DN, Lim M, Muir MK, et al. A prospective
randomised study of local versus general anaesthesia for cataract surgery.
Anaesthesia. 1993;48(5):422-428.
- Vernon SA, Cheng H. Comparison between the complications of
cataract surgery following local anaesthesia with short stay and general
anaesthesia with a five- day hospitalisation. Br J Ophthalmol.
1985;69(5):360-363.
- Magora F, Collins VJ. The influence of general anesthetic
agents on intraocular pressure in man. Arch Ophthalmol.
1962;66:806.
- Libonati MM, Complications of general anesthesia. In:
Spaeth GL, Katz LJ, eds. Current Therapy in Ophthalmic Surgery.
Philadelphia, Pa: BC Decker; 1989.
- Cunningham AJ, Barry P. Intraocular pressure physiology and
implications for anesthesia management. Can Anaesth Soc J.
1986;33:195.
- Pinhas D, Liebmann J, Ritch R. Anesthesia for glaucoma
surgery. In: Greenbaum S, ed. Ocular Anesthesia. Philadelphia, Pa: WB
Saunders Co; 1997:109-124.
- Ritch R, Liebmann JM. Sub-tenon's anesthesia for
trabeculectomy. Ophthalmic Surg. 1992;23:502-504.
- O'Donoghue E, Batterbury M, Lavy T. Effect on intraocular
pressure of local anaesthesia in eyes undergoing intraocular surgery. Br J
Ophthalmol. 1994;78(8):605-607.
- Morgan CM, Schatz H, Vine AK, et al. Ocular complications
associated with retrobulbar injections. Ophthalmology.
1988;95:660-665.
- Buys YM, Trope GE. Prospective study of sub-tenon's versus
retrobulbar anesthesia for inpatient and day-surgery trabeculectomy.
Ophthalmology. 1993;100:1585.
- Furuta M, Toriumi T, Kashiwagi K, et al. Limbal anesthesia
for cataract surgery. Ophthalmic Surg. 1990;21:22-25.
- Petersen WC, Yanoff M. Subconjunctival anesthesia: an
alternative to retrobulbar and peribulbar techniques. Ophthalmic Surg.
1991;22:199-201.
- Greenbaum S. Parabulbar anesthesia. Am J Ophthalmol.
1992;114(6):776.
- Sanford DK, Minoso y de Cal OE, Belyea DA. Response of
intraocular pressure to retrobulbar and peribulbar anesthesia. Ophthalmic
Surg Lasers. 1998;29(10):815-817.
- Singh SK, Sekhar GC, Gupta S. Etiology of ptosis after
cataract surgery. J Cataract Refract Surg. 1997;23(9):1409-1413.
- Loeffler M, Solomon LD, Renaud M. Postcataract extraction
ptosis: effect of the bridle suture [see comments]. J Cataract Refract
Surg. 1990;16(4):501-504.
- Catalano RA, Nelson LB, Calhoun JH, et al. Persistent
strabismus presenting after cataract surgery. Ophthalmology.
1987;94(5):491-594.
- Brincker P, Kessing SV. Limbus-based versus fornix-based
conjunctival flap in glaucoma filtering surgery. Acta Ophthalmol.
1992;70:641-644.
- Luntz MH, Freedman J. The fornix-based conjunctival flap in
glaucoma filtration surgery. Ophthalmic Surg. 1980;11:516.
- Reichert R, Stewart W, Shields MB. Limbus-based versus
fornix-based conjunctival flaps in trabeculectomy. Ophthalmic Surg.
1987;18:672-676.
- Shuster JN, Krupin T, Kolker AE, et al. Limbus v.
fornix-based conjunctival flap in trabeculectomy. A long-term randomized study.
Arch Ophthalmol. 1984;102:361-362.
- Traverso CE, Tomey KF, Antonios S. Limbal- vs fornix-based
conjunctival trabeculectomy flaps. Am J Ophthalmol. 1987;104:28.
- Blondeau P, Phelps CD. Trabeculectomy vs thermosclerostomy.
A randomized prospective clinical trial. Arch Ophthalmol.
1981;99:810-816.
- Shields MB. Trabeculectomy vs. full-thickness filtering
operation for control of glaucoma. Ophthalmic Surg.
1980;11:498-505.
- Iliff CE, Haas JS. Posterior lip sclerectomy. Am J
Ophthalmol. 1962;54:688.
- Marion JR, Shields MB. Thermal sclerostomy and posterior
lip sclerectomy: a comparative study. Ophthalmic Surg.
1978;9:67-75.
- Scheie HG. Retraction of scleral wound edges: A
fistulizing procedure for glaucoma. Am J Ophthalmol.
1958;45:220-229.
- Bounds GW Jr, Minton LR. Peripheral iridectomy with
scleral cautery. Am J Ophthalmol. 1964;58:84.
- Drance SM, Vargas E. Trabeculectomy and thermosclerostomy:
a comparison of two procedures. Can J Ophthalmol.
1973;8:413-415.
- Hovanesian JAD, Higginbotham EJ, Lichter PR, et al.
Long-term visual outcome of ocular hypotension after thermosclerostomy. Am J
Ophthalmol. 1993;115:603-607.
- Lewis RA, Phelps CD. Trabeculectomy vs thermosclerostomy-a
five year follow-up. Arch Ophthalmol. 1984;102:533-536.
- Abraham RK, Miller GL. Outpatient argon laser iridectomy
for angle-closure glaucoma: a two-year study. Trans Am Acad Ophthalmol
Otol. 1975;79:OP529.
- Gieser D, Wilensky J. Laser iridectomy in the management of
chronic angle-closure glaucoma. Am J Ophthalmol. 1984;98:446.
- Ritch R, Podos SM. Argon laser treatment of angle-closure
glaucoma. Perspect Ophthalmol. 1980;4:129.
- Margo CE, Groden L. Balloon cell nevus of the iris. Am
J Ophthalmol. 1986;102:282.
- Douglas WHG, Strachan IM. Surgical safety of prophylactic
peripheral iridectomy. Br J Ophthalmol. 1967;51:459.
- Luke S-K. Complications of peripheral iridectomy. Can J
Ophthalmology. 1969;4:346.
- Allen JC. Incidence of photophobia in peripheral and sector
iridectomy. Am J Ophthalmol. 1976;82:316.
- Floman N, Berson D, Landau L. Peripheral iridectomy in
closed angle glaucoma--late complications. Br J Ophthalmol.
1977;61:101.
- Godel V, Regenbogen L. Cataractogenic factors in patients
with primary angle-closure glaucoma after peripheral iridectomy. Am J
Ophthalmol. 1977;83:180.
- Krupin T, Mitchell KB, Johnson MF, et al. The long term
effects of iridectomy for primary acute angle-closure glaucoma. Am J
Ophthalmol. 1978;86:506.
- Shingleton BJ, Jacobson LM, Kuperwaser MC. Comparison of
combined cataract and glaucoma surgery using planned extracapsular and
phacoemulsification techniques. Ophthalmic Surg Lasers.
1995;26(5):414-9.
- Caprioli J, Park HJ, Weitzman M. Temporal corneal
phacoemulsification combined with superior trabeculectomy: a controlled study.
Trans Am Ophthalmol Soc. 1996;94:451-463.
- Park HJ, Weitzman M, Caprioli J. Temporal corneal
phacoemulsification combined with superior trabeculectomy. A retrospective
case-control study. Arch Ophthalmol. 1997; 115(3):318-323.
- Wyse T, Meyer M, Ruderman JM, et al. Combined
trabeculectomy and phacoemulsification: a one-site vs a two- site approach.
Am J Ophthalmol. 1998;125(3):334-339.
- Zacharia PT, Schuman JS. Combined phacoemulsification and
trabeculectomy with mitomycin-C. Ophthalmic Surg Lasers.
1997;28(9):739-744.
- Weitzman M, Caprioli J. Temporal corneal
phacoemulsification combined with separate-incision superior trabeculectomy.
Ophthalmic Surg. 1995;26(3):271-273.
- Wedrich A, Menapace R, Hirsch U, et al. Comparison of
results and complications following combined ECCE- trabeculectomy versus
small-incision-trabeculectomy and posterior chamber lens implantation. Int
Ophthalmol. 1996;20(1-3):125-129.
- Stewart WC, Crinkley CMC, Carlson AN. Results of
trabeculectomy combined with phacoemulsification versus trabeculectomy combined
with extracapsular cataract extraction in patients with advanced glaucoma.
Ophthalmic Surg. 1994;25:621-627.
- Wishart PK, Austin MW. Combined cataract extraction and
trabeculectomy: Phacoemulsification compared with extracapsular technique.
Ophthalmic Surg. 1993;24:814-821.
- Tezel G, Kolker AE, Kass MA, et al. Comparative results of
combined procedures for glaucoma and cataract: II. Limbus-based versus
fornix-based conjunctival flaps. Ophthalmic Surg Lasers.
- Berestka JS, Brown SVL. Limbus- versus fornix-based
conjunctival flaps in combined phacoemulsification and mitomycin C
trabeculectomy surgery. Ophthalmology. 1997;104:187-196.
- Nichamin LD. Enlarging the pupil for cataract extraction
using flexible nylon iris retractors. J Cataract Refract Surg.
1993;19(6):793-796.
- Fine IH. Pupilloplasty for small pupil phacoemulsification.
J Cataract Refract Surg. 1994;20(2):192-196.
- Krupin Eye Valve Filtering Surgery Study Group T. Krupin
eye valve with disk for filtration surgery. Ophthalmology.
1994;101:651-658.
- Lloyd ME, et al. Intermediate-term results of a randomized
clinical trial of the 350-mm2 vs. the 500-mm2 Baerveldt implant.
Ophthalmology. 1994;101:1456.
- Schocket SS, Lakhanpal V, Richards RD. Anterior chamber
tube shunt to an encircling band in the treatment of neovascular glaucoma.
Ophthalmology. 1982;89:1188-1194.
- Tam MYM, et al. Preliminary results of glaucoma valve
implant clinical trial. Invest Ophthalmol Vis Sci.
1994;35(Suppl):1914.
- White TC. Clinical results of glaucoma surgery using the
White glaucoma pump shunt. Ann Ophthalmol. 1992;24:365.
- Joseph NH, Sherwood MB, Trantas G, et al. A one-piece
drainage system for glaucoma surgery. Trans Ophthalmol Soc UK.
1986;105:657-664.
- Minckler DS, et al. Experimental studies of aqueous
filtration using the Molteno implant. Trans Am Ophthalmol Soc.
1987;85:368.
- Wilcox MJ, Minckler DS, Ogden TE. Pathophysiology of
artificial aqueous drainage in primate eyes with Molteno implants. J
Glaucoma. 1994;3:140.
- Francis BA, Cortes A, Chen J, et al. Characteristics of
glaucoma drainage implants during dynamic and steady- state flow conditions.
Ophthalmology. 1998;105(9):1708-1714.
- Molteno ACB. The optimal design of drainage implants for
glaucoma. Trans Ophthalmol Soc NZ. 1981;33:39.
- Wilson RP, et al. Aqueous shunts. Molteno vs Schocket.
Ophthalmology. 1992;99:672.
- Smith MF, Sherwood MB, McGorray SP. Comparison of the
double-plate Molteno drainage implant with the Schocket procedure. Arch
Ophthalmol. 1992;110:1246.
- Hodkin MJ, Goldblatt WS, Burgoyne CF, et al. Early
clinical experience with the Baerveldt implant in complicated glaucomas. Am
J Ophthalmol. 1995;120(1):32-40.
- Lloyd MAE, Baerveldt G, Heuer DK, et al. Initial clinical
experience with the Baerveldt implant in complicated glaucomas.
Ophthalmology. 1994;101:640-650.
- Freedman J, Rubin B. Molteno implant as a treatment for
refractory glaucoma in black patients. Arch Ophthalmol.
1991;109:1417-1420.
- Cooper RL. Molteno implant surgery in refractory glaucoma
[letter; comment]. Surv Ophthalmol. 1991;35(5):403.
- Lieberman MF, Ewing RH. Drainage implant surgery for
refractory glaucoma. Int Ophthalmol Clin. 1990;30(3):198-208.
- Downes RK, et al. The Molteno implant in intractable
glaucoma. Eye. 1988;2:250.
- Lotufo DG. Postoperative complications and visual loss
following Molteno implantation. Ophthalmic Surg. 1991; 22:650.
- El-Sayad F, et al. The use of releasable sutures in Molteno
glaucoma implant procedures to reduce postoperative hypotony. Ophthalmic
Surg. 1991;22:82.
- Egbert PR, Lieberman MF. Internal suture occlusion of the
Molteno glaucoma implant for the prevention of postoperative hypotony.
Ophthalmic Surg. 1989;20:53.
- Kooner KS, Goode SM. Removable ligature during Molteno
implant procedure [letter]. Am J Ophthalmol.
1992;114(1):102-103.
- Raviv T, Greenfield DS, Liebmann JM, et al. Pericardial
patch grafts in glaucoma implant surgery. J Glaucoma.
1998;7(1):27-32.
- Brandt JD. Patch grafts of dehydrated cadaveric dura mater
for tube-shunt glaucoma surgery. Arch Ophthalmol. 1993;111:1436.
- Whitson WE, Price FW Jr. Reducing hypotony after Molteno
procedure [letter; comment]. Ophthalmic Surg. 1992;23(6):434.
- Valimaki J, Tuulonen A, Airaksinen PJ. Outcome of Molteno
implantation surgery in refractory glaucoma and the effect of total and partial
tube ligation on the success rate. Acta Ophthalmol.
1998;76(2):213-9.
- Stewart W, Feldman RM, Gross RL. Collagen plug occlusion
of Molteno tube shunts. Ophthalmic Surg. 1993;24:47.
- Sherwood MB, Smith MF. Prevention of early hypotony
associated with Molteno implants by a new occluding stent technique.
Ophthalmology. 1993;100:85.
- Henderson BC. Modification of slip-knot suture for Molteno
shunt tube occlusion [letter]. Ophthalmic Surg. 1991;22(2): 113.
- Luttrull JK, Avery RL. Pars plana implant and vitrectomy
for treatment of neovascular glaucoma. Retina.
1995;15(5):379-387.
- Smiddy WE, Rubsamen PE, Grajewski A. Vitrectomy for pars
plana placement of a glaucoma seton. Ophthalmic Surg.
1994;25(8):532-535.
- Azuara-Blanco A, Katz LJ, Gandham SB, et al. Pars plana
tube insertion of aqueous shunt with vitrectomy in malignant glaucoma [letter]
[see comments]. Arch Ophthalmol. 1998;116(6):808-810.
- Varma R, Heuer DK, Lundy DC, et al. Pars plana Baerveldt
tube insertion with vitrectomy in glaucomas associated with pseudophakia and
aphakia. Am J Ophthalmol. 1995;119:401-407.
- Gandham SB, Costa VP, Katz LJ, et al. Aqueous tube-shunt
implantation and pars plana vitrectomy in eyes with refractory glaucoma. Am
J Ophthalmol. 1993;116(2):189-195.
- Lloyd M, et al. Combined Molteno implantation and pars
plana vitrectomy for neovascular glaucoma. Ophthalmology.
1991;98:1401.
- Costa VP, Spaeth GL, Eiferman RA, et al. Wound healing
modulation in glaucoma filtration surgery. Ophthalmic Surg.
1993;24:152.
- Skuta GL, Parrish RK II. Wound healing in glaucoma
filtering surgery. Surv Ophthalmol. 1987;32:149-170.
- Smith MF, Doyle JW, Nguyen QH, et al. Results of
intraoperative 5-fluorouracil or lower dose mitomycin-C administration on
initial trabeculectomy surgery. J Glaucoma. 1997;6(2):104-110.
- Singh K, Egbert PR, Byrd S, et al. Trabeculectomy with
intraoperative 5-fluorouracil vs mitomycin C. Am J Ophthalmol.
1997;123(1):48-53.
- Wilson RP, Steinmann WC. Use of trabeculectomy with
postoperative 5-fluorouracil in patients requiring extremely low intraocular
pressure levels to limit further progression. Ophthalmology.
1991;98:1047-1052.
- Whiteside-Michel J, Liebmann JM, Ritch R. Initial
5-fluorouracil trabeculectomy in young patients. Ophthalmology.
1992;99:7-13.
- Weinreb RN. Adjusting the dose of 5-fluorouracil after
filtration surgery to minimize side effects. Ophthalmology.
1987;94:564-570.
- Watanabe J, et al. Trabeculectomy with 5-fluorouracil.
Acta Ophthalmol. 1991;69:455.
- Ticho U, Ophir A. Regulating the dose of 5-fluorouracil to
prevent filtering bleb scarring. Ann Ophthalmol. 1991;23:225.
- Smith MF, et al. Results of intraoperative 5-fluorouracil
supplementation on trabeculectomy for open-angle glaucoma. Am J
Ophthalmol. 1992;114:737.
- Ruderman JM, Welch DB, Smith MF, et al. A randomized study
of 5-fluorouracil and filtration surgery. Am J Ophthalmol.
1987;104:218-224.
- Skuta GL, et al. Filtering surgery in owl monkeys treated
with the antimetabolite 5-fluorouracil 5' monophosphate entrapped in
multivesicular liposomes. Am J Ophthalmol. 1987;103:714.
- Rockwood EJ, Parrish RKI, Heuer DK, et al. Glaucoma
filtration surgery with 5-Fluorouracil. Ophthalmology.
1987;94:1071-1078.
- Rabowsky JH, Ruderman JM. Low-dose 5-fluorouracil and
glaucoma filtration surgery. Ophthalmic Surg. 1989;20:347.
- Patitsas CJ, et al. Glaucoma filtering surgery with
postoperative 5-fluorouracil patients with intraocular inflammatory disease.
Ophthalmology. 1992;99:594.
- Ophir A, Ticho U. A randomized study of trabeculectomy and
subconjunctival administration of fluorouracil in primary glaucomas. Arch
Ophthalmol. 1992;110:1072-1075.
- Krug JH, Melamed S. Adjunctive use of delayed and
adjustable low-dose 5-fluorouracil in refractory glaucoma. Am J
Ophthalmol. 1990;109:412-418.
- Kitazawa Y, et al. 5-fluorouracil for trabeculectomy in
glaucoma. Graefes Arch Clin Exp Ophthalmol. 1987;225:403.
- Heuer DK, Parrish RK, II, Gressel MG, et al.
5-fluorouracil and glaucoma filtering surgery, II, A pilot study.
Ophthalmology. 1984;91:384-394.
- Heuer DK, Parrish RK II, Gressel MG, et al. 5-fluorouracil
and glaucoma filtering surgery. III. Intermediate follow-up of a pilot study.
Ophthalmology. 1986;93:1537-1546.
- Fluorouracil Filtering Surgery Study Group T. Fluorouracil
filtering surgery study one year follow-up. Am J Ophthalmol.
1989;108:625-635.
- Fluorouracil Filtering Surgery Study Group T. Three-year
follow-up of the fluorouracil filtering surgery study. Am J Ophthalmol.
1993;115:82-92.
- Fluorouracil filtering surgery study group T. Five-year
follow-up of the fluorouracil filtering surgery study. Am J Ophthalmol.
1996;121:349-366.
- Dietze PJ, Feldman RM, Gross RL. Intraoperative application
of 5-fluorouracil during trabeculectomy. Ophthalmic Surg.
1992;23:662.
- Falck FY, Skuta GL, Klein TB. Mitomycin versus
5-fluorouracil antimetabolite therapy for glaucoma filtration surgery. Semin
Ophthalmol. 1992;7:97.
- Tahery MM, Lee DA. Review: Pharmacologic control of wound
healing in glaucoma filtration surgery. J Ocular Pharmacol.
1989;5:155.
- Egbert PR, Williams AS, Singh K, et al. A prospective
trial of intraoperative fluorouracil during trabeculectomy in a black
population. Am J Ophthalmol. 1993;116:612-616.
- Lanigan L, Stürmer J, Baez KA, et al. Single
intraoperative applications of 5-fluorouracil during filtration surgery: early
results. Br J Ophthalmol. 1994;78:33-37.
- Letchinger SL, Becker B, Wax MB. The effects of
subconjunctival administration of mitomycin C on intraocular pressure in
rabbits. Invest Ophthalmol Vis Sci. 1992;33(Suppl):736.
- Derick RJ, et al. Potential toxicity of mitomycin-C.
Arch Ophthalmol. 1991;109:1635.
- Peyman GA, Greenberg BS, Fishman GA. Evaluation of
toxicity of intravitreal antineoplastic drugs. Ophthalmic Surg.
1984;15:411-413.
- Gupta S, Basti S. Corneoscleral, ciliary body, and
vitreoretinal toxicity after excessive instillation of Mitomycin-C. Am J
Ophthalmol. 1992;114:503.
- Khaw PT, et al. Prolonged localized tissue effects from 5
minute exposures to fluorouracil and mitomycin-C. Arch Ophthalmol.
1993;111:263.
- Khaw PT, et al. The long-term effects of 5-fluorouracil
and sodium butyrate on human Tenon's capsule fibroblasts. Invest Ophthalmol
Vis Sci. 1992;33:2043.
- Khaw PT, et al. 5-minute treatments with fluorouracil,
floxuridine and mitomycin have long-term effects on human Tenon's capsule
fibroblasts. Arch Ophthalmol. 1992;110:1150.
- Scott IU, Greenfield DS, Schiffman J, et al. Outcomes of
primary trabeculectomy with the use of adjunctive mitomycin. Arch
Ophthalmol. 1998;116(3):286-291.
- Chen CW. Enhanced intraocular pressure controlling
effectiveness of trabeculectomy by local application of mitomycin-C. Trans
Asia-Pacific Acad Ophthalmol. 1983;9:172.
- Skuta GL, Beeson CC, Higginbotham EJ. Intraoperative
mitomycin versus postoperative 5-fluorouracil in high-risk glaucoma filtering
surgery. Ophthalmology. 1992;99:438-444.
- Beeson C, et al. Randomized clinical trial of
intraoperative subconjunctival mitomycin-c versus postoperative 5-fluorouracil.
Invest Ophthalmol Vis Sci. 1991;32:1122.
- Kitazawa Y, Kawase K, Matsushita H, et al. Trabeculectomy
with mitomycin: a comparative study with fluorouracil. Arch Ophthalmol.
1991;109:1693-1698.
- Robin AL, Ramakrishnan R, Krishnadas R, et al. A long-term
dose-response study of mitomycin in glaucoma filtration surgery [see comments].
Arch Ophthalmol. 1997;115(8):969-974. 1998;24:352-360.
- Costa VP, Moster MR, Wilson RP, et al. Effects of topical
mitomycin C on primary trabeculectomies and combined procedures. Br J
Ophthalmol. 1993;77:693-697.
- Kitazawa Y, Suemori-Matsushita H, Yamamoto T, et al.
Low-dose and high-dose mitomycin trabeculectomy as an initial surgery in
primary open-angle glaucoma. Ophthalmology. 1993;100:1624-1628.
- Mermoud A, et al. Trabeculectomy with mitomycin-C for
refractory glaucoma in blacks. Am J Ophthalmol. 1993; 116:72.
- Neelakantan A, et al. Effect of the concentration and
duration of application of mitomycin C in trabeculectomy. Ophthalmic
Surg. 1994;25:612-615.
- Palmer SS. Mitomycin as adjunct chemotherapy with
trabeculectomy. Ophthalmology. 1991;98:317-321.
- Mietz H, Krieglstein GK. Three-year follow-up of
trabeculectomies performed with different concentrations of mitomycin-C.
Ophthalmic Surg Lasers. 1998;29(8):628-634.
- Lee JJ, Park KH, Youn DH. The effect of low-and high-dose
adjunctive mitomycin C in trabeculectomy. Korean J Ophthalmol.
1996;10(1):42-47.
- Megevand GS, Salmon JF, Scholtz RP, et al. The effect of
reducing the exposure time of mitomycin C in glaucoma filtering surgery.
Ophthalmology. 1995;102(1):84-90.
- Singh J, O'Brien C, Chawla HB. Success rate and
complications of intraoperative 0. 2 mg/ml mitomycin C in trabeculectomy
surgery. Eye. 1995;9:460-466.
- Lee DA, Hersh P, Kersten D, et al. Complications of
subconjunctival 5-fluorouracil following glaucoma filtration surgery.
Ophthalmic Surg. 1987;18:187-190.
- Chen C, Huang H, Bair JS, et al. Trabeculectomy with
simultaneous topical application of Mitomycin-C in refractory glaucoma. J
Ocular Pharmacol. 1990;6:175-182.
- Franks WA, Hitchings RA. Complications of 5-fluorouracil
after trabeculectomy. Eye. 1991;5:385-389.
- Jampel HD, Pasquale LR, DiBernardo C. Hypotony maculopathy
following trabeculectomy with mitomycin C. Arch Ophthalmol.
1992;110:1049-1050.
- Stamper RL, McMenemy MG, Lieberman MF. Hypotonous
maculopathy after trabeculectomy with subconjunctival 5-fluorouracil. Am J
Ophthalmol. 1992;114:544-553.
- Zacharia PT, Deppermann SR, Schuman JS. Ocular hypotony
after trabeculectomy with mitomycin C. Am J Ophthalmol.
1993;116:314-326.
- Dellaporta A. Fundus changes in postoperative hypotony.
Am J Ophthalmol. 1955;40:781-785.
- Gass JDM, Hypotony maculopathy. In: Bellows JG, ed.
Contemporary Ophthalmology. Baltimore, Md: Williams and Wilkins;
1972.
- Suner IJ, Greenfield DS, Miller MP, et al. Hypotony
maculopathy after filtering surgery with mitomycin C. Incidence and treatment
[see comments]. Ophthalmology. 1997;104(2): 207-214; discussion
214-215.
- Altan T, Temel A, Bavbek T, et al. Hypotonic maculopathy
after trabeculectomy with postoperative use of 5-fluorouracil.
Ophthalmologica. 1994;208(6):318-320.
- Shields MB, Scroggs MW, Sloop MW, et al. Clinical and
histopathologic observations concerning hypotony after trabeculectomy with
adjunctive mitomycin-C. Am J Ophthalmol. 1993;116:673-683.
- Costa VP, Wilson RP, Moster MR, et al. Hypotony
maculopathy following the use of topical mitomycin-C in glaucoma surgery.
Ophthalmic Surg. 1993;24:389-94.
- Wolner B, Liebmann JM, Sassani JW, et al. Late
bleb-related endophthalmitis after trabeculectomy with adjunctive
5-fluorouracil. Ophthalmology. 1991;98:1053-1060.
- Mochizuki M, Jikihara S, Ando Y, et al. Incidence of
delayed onset infection after trabeculectomy with adjunctive mitomycin C or
5-fluorouracil treatment. Br J Ophthalmol. 1997;81:877-883.
- Greenfield DS. Bleb-related ocular infection. J
Glaucoma. 1998;7(2):132-136.
- Ayyala RS, Bellows AR, Thomas JV, et al. Bleb infections:
clinically different courses of "blebitis" and endophthalmitis. Ophthalmic
Surg Lasers. 1997;28(6):452-60.
- Greenfield DS, Suner IJ, Miller MP, et al. Endophthalmitis
after filtering surgery with mitomycin C. Arch Ophthalmol.
1996;114:943-949.
- Higginbotham EJ, Stevens RK, Musch DC, et al. Bleb-related
endophthalmitis after trabeculectomy with mitomycin C. Ophthalmology.
1996;103:650-656.
- Phillips WB, Wong TP, Berger RL, et al. Late-onset
endophthalmitis associated with filtering blebs. Ophthalmic Surg.
1994;25:88-91.
- Yaldo MK, Stamper RL. Long-term effects of mitomycin on
filtering blebs. Lack of fibrovascular proliferative response following severe
inflammation. Arch Ophthalmol. 1993; 111:824-826.
- Belyea DA, Dan JA, Stamper RL, et al. Late onset of
sequential multifocal bleb leaks after glaucoma filtration surgery with
5-fluorouracil and mitomycin C. Am J Ophthalmol. 1997;124:40-45.
- Brown RH, et al. Treatment of bleb infection after
glaucoma surgery. Arch Ophthalmol. 1994;112:57-61.
- Mandelbaum S, Forster RK, Gelende H, et al. Late onset
endophthalmitis associated with filtering blebs. Ophthalmology.
1985;92:964-972.
- Susanna R, Jr. , Takahashi W, Nicolela M. Late bleb leakage
after trabeculectomy with 5-fluorouracil or mitomycin C. Can J
Ophthalmol. 1996;31:296-300.
- Iliff CE. Flap perforation in glaucoma surgery sealed by a
tissue patch. Arch Ophthalmol. 1964;71:215-218.
- Brown SVL. Management of a partial-thickness scleral-flap
buttonhole during trabeculectomy. Ophthalmic Surg.
1994;25:732-733.
- Alpar JJ. Sodium hyaluronate (HealonR) in glaucoma
filtering procedures. Ophthalmic Surg. 1986;17:724.
- Barak A, Alhalel A, Kotas R, et al. The protective effect
of early intraoperative injection of viscoelastic material in trabeculectomy.
Ophthalmic Surg. 1992;23:206-209.
- Raitta C, Lehto I, Puska P, et al. A randomized,
prospective study on the use of sodium hyaluronate (Healon) in trabeculectomy
[see comments]. Ophthalmic Surg. 1994;25(8):536-539.
- Wand M. Viscoelastic agent and the prevention of
post-filtration flat anterior chamber. Ophthalmic Surg.
1988;19:523-524.
- Hung SO. Role of sodium hyaluronate (Healon) in triangular
flap trabeculectomy. Br J Ophthalmol. 1985;69:46-50.
- Teekhasaenee C, Ritch R. The use of PhEA 34c in
trabeculectomy. Ophthalmology. 1986;93:487-491.
- Liebmann JM, Ritch R, DiSclafani M, et al. Early
intraocular pressure rise after trabeculectomy. Arch Ophthalmol.
1990;108:1549-1552.
- Spaeth GL. Suprachoroidal hemorrhage: no longer a disaster.
Ophthalmic Surg. 1987;18:329.
- Taylor DM. Expulsive hemorrhage: some observations and
comments. Trans Am Ophthalmol Soc. 1974;82:157.
- Welch JC, Spaeth GL, Benson WE. Massive suprachoroidal
hemorrhage: Follow-up and outcome of 30 cases. Ophthalmology.
1988;95:1202-1206.
- Speaker MG, Guerriero PN, Met JA, et al. A case-control
study of risk factors for intraoperative suprachoroidal expulsive hemorrhage.
Ophthalmology. 1991;98:202-210.
- Speaker MG, Guerriero PN, Met JA, et al. A case-control
study of risk factors for intraoperative suprachoroidal expulsive hemorrhage.
Ophthalmology. 1991;98:202-210.
- Canning CR, Lavin M, McCartney ACE, et al. Delayed
suprachoroidal haemorrhage after glaucoma operations. Eye.
1989;3:327-331.
- Givens K, Shields MB. Suprachoroidal hemorrhage after
glaucoma filtering surgery. Am J Ophthalmol. 1987;103:689-694.
- Gressel MG, Parrish RK, II, Heuer DK. Delayed nonexpulsive
suprachoroidal hemorrhage. Arch Ophthalmol. 1984;102:1757-1760.
- Fluorouracil Filtering Surgery Study Group T. Risk factors
for suprachoroidal hemorrhage after filtering surgery. Am J Ophthalmol.
1992;113:501-507.
- Ruderman JM, Harbin TS, Jr. , Campbell DG. Postoperative
suprachoroidal hemorrhage following filtration procedures. Arch
Ophthalmol. 1986;104:201-205.
- Ariano ML, Ball SF. Delayed nonexpulsive suprachoroidal
hemorrhage after trabeculectomy. Ophthalmic Surg.
1987;18:661-666.
- Frenkel REP, Shin DH. Prevention and management of delayed
suprachoroidal hemorrhage after filtration surgery. Arch Ophthalmol.
1986;104:1459-1463.
- Brubaker RF. Intraocular surgery and choroidal hemorrhage.
Arch Ophthalmol. 1984;102:1753-1754.
- Lambrou FH, Jr. , Meredith TA, Kaplan HJ. Secondary
surgical management of expulsive choroidal hemorrhage. Arch Ophthalmol.
1987;105:1195-1198.
- Lakhanpal V, Schocket SS, Elman MJ, et al. A new modified
vitreoretinal surgical approach in the management of massive suprachoroidal
hemorrhage. Ophthalmology. 1989;96:793-800.
- Reynolds MG, Haimovici R, Flynn HW, Jr. , et al.
Suprachoroidal hemorrhage. Clinical features and results of secondary surgical
management. Ophthalmology. 1993; 100:460-465.
- Chu TG, et al. Massive suprachoroidal hemorrhage with
central retinal apposition. A clinical and echographic study. Arch
Ophthalmol. 1991;109:1575-1581.
- Portney GL. Trabeculectomy and postoperative ocular
hypertension in secondary angle-closure glaucoma. Am J Ophthalmol.
1977;84:145.
- Cohn JH, Aron-Rosa D. Reopening blocked trabeculectomy
sites with the YAG laser. Am J Ophthalmol. 1984;102:1024.
- Dailey RA, Samples JR, Van Buskirk EM. Reopening
filtration fistulas with neodymium-YAG laser. Am J Ophthalmol.
1986;102:491.
- Ofner S, Smith TJ. Neodymium:YAG laser for the treatment
of encapsulated blebs after filtration surgery. Am J Ophthalmol.
1988;106:232-234.
- Praeger DL. The reopening of closed filtering blebs using
the neodymium:YAG laser. Ophthalmology. 1984;91:373.
- Ruben S, Tsai J, Hitchings RA. Malignant glaucoma and its
management. Br J Ophthalmol. 1997;81(2):163-7.
- Little BC, Hitchings RA. Pseudophakic malignant glaucoma:
Nd:YAG capsulotomy as a primary treatment. Eye. 1993; 7:102-104.
- Melamed S, Ashkenazi I, Blumenthal M. Nd-YAG laser
hyaloidotomy for malignant glaucoma following one-piece 7 mm intraocular lens
implantation. Br J Ophthalmol. 1991;75:501.
- Tsai JC, Barton KA, Miller MH, et al. Surgical results in
malignant glaucoma refractory to medical or laser therapy. Eye.
1997;11(Pt 5):677-681.
- Johnson DH. Options in the management of malignant glaucoma
[editorial; comment]. Arch Ophthalmol. 1998;116 (6):799-800.
- Cekic O, Batman C. Pars plana vitrectomy in the treatment
of phakic and pseudophakic malignant glaucoma [letter; comment]. Arch
Ophthalmol. 1998;116(1):118.
- Bellows AR, Chylack JR, Hutchinson BT. Choroidal
detachment: Clinical manifestation, therapy and mechanism of formation.
Ophthalmology. 1981;88:1107-1115.
- Berke SJ, Bellows AR, Shingleton BJ, et al. Chronic and
recurrent choroidal detachment after glaucoma filtering surgery.
Ophthalmology. 1987;94:154-162.
- Burney EN, Quigley MA, Robin AL. Hypotony and choroidal
detachment as late complications of trabeculectomy. Am J Ophthalmol.
1987;103:685.
- Newhouse RP, Beyrer C. Hypotony as a late complication of
trabeculectomy. Ann Ophthalmol. 1982;14:685.
- Greenfield DS, Liebmann JM, Jee J, et al. Late-onset bleb
leaks after glaucoma filtering surgery. Arch Ophthalmol.
1998;116:443-447.
- Cohen JS, Shaffer RN, Hetherington J Jr, et al. Revision
of filtration surgery. Arch Ophthalmol. 1977;95:1612-1615.
- Galin MA, Hung PT. Surgical repair of leaking blebs. Am
J Ophthalmol. 1977;83:328-333.
- Romanchuk KG. Seidel's test using 10% fluorescein. Can J
Ophthalmol. 1979;14:253.
- Cain WJ, Sinskey RM. Detection of anterior chamber leakage
with Seidel's test. Arch Ophthalmol. 1981;99:2013.
- Tomlinson CP, Belcher CD 3rd, et al. Management of leaking
filtration blebs. Ann Ophthalmol. 1987;19:405-411.
- Petursson GJ, Fraunfelder FT. Repair of an inadvertent
buttonhole or leaking filtering bleb. Arch Ophthalmol.
1979;97:926-927.
- Melamed S, Hersh P, Kersten D, et al. The use of glaucoma
shell tamponade in leaking filtration blebs. Ophthalmology.
1986;93:839-842.
- Hill RA, Aminlari A, Sassani JW, et al. Use of a
symblepharon ring for treatment of over-filtration and leaking blebs after
glaucoma filtration surgery. Ophthalmic Surg. 1990; 21:707-710.
- O'Sullivan F, Dalton R, Rostron CK. Fibrin glue: an
alternative method of wound closure in glaucoma surgery. J Glaucoma.
1996;5(6):367-70. 1998;24:352-360.
- Katz LJ. Ciliochoroidal detachment. Ophthalmic Surg.
1987;18:1775.
- Brubaker RF, Pederson JE. Ciliochoroidal detachment.
Surv Ophthalmol. 1983;27:281.
- Osher RH, Cionni RJ, Cohen JS. Re-forming the flat anterior
chamber with Healon. J Cataract Refract Surg. 1996;
22(4):411-415.
- Hattenhauer JM, Lipsich MP. Late endophthalmitis after
filtering surgery. Am J Ophthalmol. 1971;72:1097-1101.
- Katz LJ, Cantor LB, Spaeth GL. Complications of surgery in
glaucoma: early and late bacterial endophthalmitis following glaucoma filtering
surgery. Ophthalmology. 1985;92:959.
- Ritch R, Schuman JS, Belcher CD, III. Management of the
leaking filtration bleb. J Glaucoma. 1993;2:114-118.
- Tester R, Olson RJ, Pace NL, Samore M. Dysphotopsia in
phakic and pseudophakic patients--incidence and relation to intraocular lens
types. J Cataract Refract Surg. 2000;26:810-816.
- Blok MDW, Kok JHC, van Mil C, et al. Use of the Megasoft
bandage lens for treatment of complications after trabeculectomy. Am J
Ophthalmol. 1990;110:264-268.
- Kirk HQ. Cauterization of filtering blebs following
cataract extraction. Trans Am Acad Ophthalmol Otolaryngol.
1973;77:573.
- Baum M, Weiss HS. Argon laser closure of conjunctival bleb
leak. Arch Ophthalmol. 1993;111:438.
- Hennis HL, Stewart WC. Use of the argon laser to close
filtering bleb leaks. Graefes Arch Clin Exp Ophthalmol. 1992;
230:537-541.
- Oz MC, Johnson JP, Parangi S, et al. Tissue soldering by
use of indocyanine green dye-enhanced fibrinogen with the near infrared diode
laser. J Vasc Surg. 1990;11:718-725.
- Yannuzzi LA, Theodore FH. Cryotherapy of post-cataract
blebs. Am J Ophthalmol. 1973;76(2):217-222.
- Wright MM, Brown EA, Maxwell K, et al. Laser-cured
fibrinogen glue to repair bleb leaks in rabbits. Arch Ophthalmol.
1998;116(2):199-202.
- Kosmin AS, Wishart PK. A full-thickness scleral graft for
the surgical management of a late filtration bleb leak. Ophthalmic Surg
Lasers. 1997;28(6):461-468.
- Asrani SG, Wilensky JT. Management of bleb leaks after
glaucoma filtering surgery. Use of autologous fibrin tissue glue as an
alternative. Ophthalmology. 1996;103(2):294-298.
- Smith MF, Magauran RG, III, Betchkal J, et al. Treatment
of postfiltration bleb leaks with autologous blood. Ophthalmology.
1995;102:868-871.
- Wilson MR, Kotas-Neumann R. Free conjunctival patch for
repair of persistent late bleb leak. Am J Ophthalmol.
1994;117:569-574.
- Pederson JE, Ocular hypotony. In: Ritch R, Shields MB,
Krupin T, eds. The Glaucomas. St Louis, Mo: CV Mosby Co; 1989.
- Cohen SM, Flynn HW Jr, Palmberg PF, et al. Treatment of
hypotony maculopathy after trabeculectomy. Ophthalmic Surg Lasers.
1995;26(5):435-441.
- Schwartz GF, Robin AL, Wilson RP, et al. Resuturing the
scleral flap leads to resolution of hypotony maculopathy. J Glaucoma.
1996;5(4):246-251.
- Duker JS, Schuman JS. Successful surgical treatment of
hypotony maculopathy following trabeculectomy with topical mitomycin C.
Ophthalmic Surg. 1994;25(7):463-465.
- Keroub C, Hyams SW, Rath E. Study of cataract formation
following trabeculectomy. Glaucoma. 1984;6:117.
- Sugar HS. Cataract formation and refractive changes after
surgery for angle-closure glaucoma. Am J Ophthalmol.
1970;69:747.
- Chen TC, Wilensky JT, Viana MA. Long-term follow-up of
initially successful trabeculectomy. Ophthalmology.
1997;104(7):1120-1125.
- Parrish RK, II, Herschler J. Eyes with end-stage
neovascular glaucoma; natural history following successful modified filtering
operation. Arch Ophthalmol. 1983;101:745-746.
- Merritt JC. Filtering procedures in American blacks.
Ophthalmic Surg. 1980;11:91-94.
- Bellows AR, Johnstone MA. Surgical management of chronic
glaucoma in aphakia. Ophthalmology. 1983;90:807-813.
- Herschler J. Medically uncontrolled glaucoma in the
aphakic eye. Ann Ophthalmol. 1981;13:909.
- Heuer DK, Gressel MG, Parrish RK, II, et al.
Trabeculectomy in aphakic eyes. Ophthalmology.
1984;91:1045-1051.
- Schwartz AL, Anderson DR, Glaucoma surgery in aphakia. In:
Emery JM, Paton D, eds. Current Concepts in Cataract Surgery. St Louis,
Mo: CV Mosby Co; 1974.
- Shirato S, Kitazawa Y, Mishima S. A critical analysis of
the trabeculectomy results by a prospective follow-up design. Jpn J
Ophthalmol. 1982;26:468-480.
- Liebmann J, Ritch R. Management of the failing filtering
bleb. Semin Ophthalmol. 1991;6:1-6.
- Stewart WC, Shields MB, Miller KN, et al. Early
postoperative prognostic indicators following trabeculectomy. Ophthalmic
Surg. 1991;22:23-26.
- Wieland M, Spaeth GL. Use of digital compression following
glaucoma surgery. Ophthalmic Surg. 1988;19:350-352.
- Brown RH, Lynch MG. Ab-Interno filtering surgery, internal
sclerectomy with the trabecuphine. Ophthalmol Clin N Am.
1988;1:199.
- Brown RM, et al. Internal sclerectomy for glaucoma
filtering surgery with automated trephine. Arch Ophthalmol.
1987;105:133-6.
- Feldman RM, et al. Risk factors for the development of
Tenon's capsule cysts after trabeculectomy. Ophthalmology.
1989;96:336-341.
- Ophir A. Encapsulated filtering bleb. A selective
review-new deductions. Eye. 1992;6:348-352.
- Pederson JE, Smith SG. Surgical management of encapsulated
filtering blebs. Ophthalmology. 1985;92:955-958.
- Richter CU, et al. The development of encapsulated
filtering blebs. Ophthalmology. 1988;95:1163-1168.
- Sherwood MB, et al. Cysts of Tenon's capsule following
filtration surgery. Medical management. Arch Ophthalmol.
1987;105:1517-1521.
- Campagna JA, Munden PM, Alward WL. Tenon's cyst formation
after trabeculectomy with mitomycin C. Ophthalmic Surg.
1995;26(1):57-60.
- Scott DR, Quigley HA. Medical management of a high bleb
phase after trabeculectomies. Ophthalmology. 1988;95:1169.
- Ewing RH, Stamper RL. Needle revision with and without
5-fluorouracil for the treatment of failed filtering blebs. Am J
Ophthalmol. 1990;110:254-259.
- Potash SD, Ritch R, Liebmann J. Ocular hypotony and
choroidal effusion following bleb needling. Ophthalmic Surg.
1993;24:279.
- Shin DH, Juzych MS, Khatana AK, et al. Needling revision of
failed filtering blebs with adjunctive 5-fluorouracil. Ophthalmic Surg.
1993;24:242-248.
- Mardelli PG, Lederer CM Jr, Murray PL, et al. Slit-lamp
needle revision of failed filtering blebs using mitomycin C.
Ophthalmology. 1996;103:1946-1955.
- Greenfield DS, Miller MP, Suner IJ, et al. Needle
elevation of the scleral flap for failing filtration blebs after trabeculectomy
with mitomycin C. Am J Ophthalmol. 1996;122:195-204.
- Apostolov VI, Siarov NP. Subconjunctival injection of
low-dose Mitomycin-C for treatment of failing human trabeculectomies. Int
Ophthalmol. 1996;20(1-3):101-105.
- Gillies WE, Brooks AMV. Restoring the function of the
failed bleb. Aust NZ J Ophthalmol. 1991;19:49-51.
- Morales J, Ritch R. Treatment of failing filtering blebs.
Clin Decisions Ophthalmol. 1987;11:4-11.
- Tabbara KF. Late infections following filtering
procedures. Ann Ophthalmol. 1976;8:1228-1231.
- Nguyen QH, Budenz DL, Parrish RK, 2nd. Complications of
Baerveldt glaucoma drainage implants. Arch Ophthalmol.
1998;116(5):571-575.
- Melamed S, et al. Postoperative complications after
Molteno implant surgery. Am J Ophthalmol. 1991;111:319.
- Dugel PR, Heuer DK, Thach AB, et al. Annular peripheral
choroidal detachment simulating aqueous misdirection after glaucoma surgery.
Ophthalmology. 1997;104:439-444.
- Paysse E, Lee PP, Lloyd MA, et al. Suprachoroidal
hemorrhage after Molteno implantation. J Glaucoma.
1996;5(3):170-175.
- Heher KL, et al. Late-onset sterile endophthalmitis after
Molteno tube implantation. Am J Ophthalmol. 1992;114:771.
- Lieberman MF. Late infectious endophthalmitis from exposed
glaucoma setons [letter; comment]. Arch Ophthalmol.
1992;110(12):1685.
- Fanous MM, Cohn RA. Propionibacterium endophthalmitis
following Molteno tube repositioning. J Glaucoma.
1997;6(4):201-202.
- Krebs DB, Liebmann JM, Ritch R, et al. Late infectious
endophthalmitis from exposed glaucoma setons. Arch Ophthalmol.
1992;110:174-175.
- Brown RD, Cairns JE. Experience with the Molteno long tube
implant. Trans Ophthalmol Soc UK. 1983;102:51.
- Minckler DS, et al. Clinical experience with the
single-plate Molteno implant in complicated glaucomas. Ophthalmology.
1988;95:1181.
- Sherwood MB, Joseph NH, Hitchings RA. Surgery for
refractory glaucoma: results and complications with a modified Schocket
technique. Arch Ophthalmol. 1987;105:562.
- Sidoti PA, et al. Epithelial ingrowth and glaucoma
drainage implants. Ophthalmology. 1994;101:872.
- Traverso CE, Tomey KF, Al-Kaff A. The long-tube single
plate Molteno implant for the treatment of refractory glaucomas. Int
Ophthalmol. 1989;13:159.
- Fiore PM, Melamed S. Use of neodymium:YAG laser to open an
occluded Molteno tube. Ophthalmic Surg. 1989;20:201.
- Oram O, Gross RL, Severin TD, et al. Opening an occluded
Molteno tube with the picosecond neodymium-yttrium lithium fluoride laser.
Arch Ophthalmol. 1994;112:1023.
- Tessler Z, Jluchoded S, Rosenthal G. Nd:YAG laser for
Ahmed tube shunt occlusion by the posterior capsule. Ophthalmic Surg
Lasers. 1997;28(1):69-70.
- Krawitz PL. Treatment of distal occlusion of Krupin eye
valve with disk using cannular flush. Ophthalmic Surg.
1994;25:102.
- Classen L, Kivela T, Tarkkanen A. Histopathologic and
immunohistochemical analysis of the filtration bleb after unsuccessful glaucoma
seton implantation. Am J Ophthalmol. 1996;122(2):205-12.
- Chen PP, Palmberg PF. Needling revision of glaucoma
drainage device filtering blebs [published erratum appears in Ophthalmology.
1997;104(10):1532] [see comments]. Ophthalmology.
1997;104(6):1004-10.
- Frank JW, Perkins TW, Kushner BJ. Ocular motility defects
in patients with the Krupin valve implant. Ophthalmic Surg.
1995;26(3):228-32.
- Smith SL, et al. Early clinical experience with the
Baerveldt 350-mm2 glaucoma implant and associated extraocular muscle imbalance.
Ophthalmology. 1993;100:914.
- Munoz M, Parrish RK, II. Strabismus following implantation
of Baerveldt devices. Arch Ophthalmol. 1993;111:1096.
- Kooner KS, Cavanagh HD, Zimmerman CF, et al. Eye movement
restrictions after Molteno implant surgery [letter]. Ophthalmic Surg.
1993;24(7):498-499.
- Ball SF, Herrington RG, Liang K. Brown's superior oblique
tendon syndrome after Baerveldt glaucoma implant. Arch Ophthalmol.
1992;110:1368.
- Christmann LM, Wilson ME. Motility disturbances after
Molteno implants. J Pediatr Ophthalmol Strabismus. 1992;29:44.
- Prata JA Jr , Minckler DS, Green RL. Pseudo-Brown's
syndrome as a complication of glaucoma drainage implant surgery. Ophthalmic
Surg. 1993;24:608.
- Dobler AA, et al. Acquired Brown's syndrome after a
double-plate Molteno implant. Am J Ophthalmol. 1993;116:641.
- Cardakli UF, Perkins TW. Recalcitrant diplopia after
implantation of a Krupin valve with disc. Ophthalmic Surg.
1994;25:256-258.
- Wilson-Holt N, et al. Hypertropia following inferiorly
sited double plated Molteno tubes. Ophthalmology. 1990;
109(Suppl):143.
- Roth SM, Spaeth GL, Starita RJ, et al. The effects of
postoperative corticosteroids on trabeculectomy and the clinical course of
glaucoma: Five-year follow-up study. Ophthalmic Surg.
1991;22:724-729.