Introduction
Keratoconus is a progressive disorder of noninflammatory corneal thinning in which the stroma assumes a conical shape, leading to myopia and irregular astigmatism, and mild-to-marked impairment in quality of vision. Breaks in Bowman's layer, deposition of iron in the basal layers of the corneal epithelium, and stromal thinning comprise the hallmark triad of keratoconus. The condition usually affects both eyes, although asymmetric involvement may exist. Onset is typically at puberty with progression until the third or fourth decade of life; however, the condition may commence later in life or arrest at any age. Commonly recognized associations include Down syndrome, Leber's congenital amaurosis, and connective tissue disorders, although keratoconus is most commonly an isolated condition. Atopy, mechanical trauma from eye rubbing, and hard contact lens use have also been associated with keratoconus, and 6% to 8% of patients show evidence of familial transmission. Incidence varies between 50 and 230 per 100,000 in the general population, across all ethnic groups, with no male or female preponderance.1 Laboratory studies suggest a role for degradative enzymes and proteinase inhibitors, and a possible role for the interleukin-1 system and apoptosis in its pathogenesis, but these roles must be more clearly defined. Genes suggested by these studies, as well as collagen genes and their regulatory products, could be used as potential candidate genes to study patients with familial keratoconus.2-4 Other hypotheses being studied include the build-up of destructive aldehydes or peroxynitrites within the cornea, the abnormal processing of free radicals, leading to poor wound healing and stromal thinning, and fibrosis.5 It may be difficult to distinguish keratoconus from other ectatic dystrophies and thinning disorders, such as pellucid marginal degeneration, Terrien's marginal degeneration, and keratoglobus, but the management and prognosis of these disorders differ markedly from keratoconus.
Clinical Features
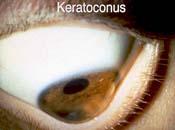
Clinical signs of keratoconus include stromal thinning (central, paracentral, inferior, or inferotemporal), conical protrusion, an iron line surrounding the cone (Fleischer's ring), fine vertical stress lines in the deep stroma and Descemet's membrane that parallel the axis of the cone and disappear transiently on gentle digital pressure (Vogt's striae). Other accompanying signs may include epithelial nebulae, anterior stromal scars, enlarged corneal nerves, and increased intensity of the corneal endothelial reflex and subepithelial fibrillary lines. Munson's sign is a V-shaped conformation of the lower lid produced by the ectatic cornea in downgaze (Slide 1). Rizzuti's sign is a sharply focused beam of light near the nasal limbus produced by lateral illumination of the cornea in patients with advanced keratoconus. Scissoring of the retinoscopic reflex or the "Charleux" oil droplet sign is sometimes present on retroillumination. Patients with advanced disease may occasionally present with a sudden onset of visual loss accompanied by pain. The conjunctiva may be injected and a diffuse stromal opacity noted in the cornea. This condition, known as "hydrops," is caused by breaks in Descemet's membrane with stromal imbibition of aqueous through these breaks. Endothelium grows anterior and posterior to denuded Descemet's membrane and integrity is usually established 3 to 4 months after the acute event.
Computer-Assisted Videokeratography
Until recently, photokeratoscopes such as the nine-ring placido disk reflections were used to detect keratoconus by compression of the mires inferiorly or inferotemporally into the shape of an egg. Computer-assisted videokeratoscopes, which generate color-coded maps and topographic indices, are currently the most sensitive device to detect the forme fruste of keratoconus (Slide 2).6 The condition appears as an area of concentric zones of decreasing power. Topographic data points in polar coordinates using 256 radial lines scanning across 25 rings are examined, and 7,000 data points are generated. Three features are common to keratoconus videokeratographs that use spherically biased algorithms (sagittal topography): a localized area of increased power, inferior-superior power asymmetry with a bow-tie pattern, and skewed steep radial axes above and below the horizontal meridian (depicting irregular astigmatism, the hallmark of keratoconus).
Treatment
Contact lenses are the mainstay of therapy in keratoconus. Early in the disease, soft lenses of the toric design are adequate. As the disease progresses, more complex rigid gas permeable lenses are used, including multicurved spherical-based lenses, aspheric lenses, and bispheric lenses.7 A hybrid lens, which has a rigid central portion for obtaining the best optics and a soft hydrophilic peripheral skirt, is popular with some practitioners. Common complications from lenses include induced corneal abrasion, apical scarring, neovascularization from induced hypoxia, lens discomfort, and lens displacement from poor fitting. Although some reports suggest that rigid contact lenses induce keratoconus and anecdotal reports contend that keratoconus may be arrested by good contact lens fitting, neither of these contentions can be supported from the current evidence.
A corneal transplant may be indicated if there is blurred vision with central scarring or intolerance to contact lenses. Although the reported success rates are high (93% to 96%),8-10 visual recovery may take as long as 6 months and there is still a 50% chance that contact lenses may be required, either because of residual myopia or postkeratoplasty astigmatism. Using donor and host trephines of equal size (usually 7.5 mm) and a combination of relaxing incisions and compression sutures with the aid of topography helps reduce residual refractive error. There have been isolated reports of keratoconus occurring decades after surgery, but it is not clear if keratoconus recurred in the graft or whether there was mild, undetected keratoconus in the donor buttons.11
Although good long-term results have been reported for epikeratoplasty, this procedure has, for the most part, been abandoned in favor of penetrating keratoplasty because of the superior quality of vision afforded by the latter procedure.12 Excimer laser phototherapeutic keratectomy has been used for removing nodular subepithelial scars, but is not widely accepted because of the potential risk for posterior corneal ectasia in an already thinned cornea.
Recently, intrastromal corneal rings have been inserted in patients with keratoconus (Slide 3). After topical anesthesia and sterile preparation, a small, modified lateral corneal incision is made and then two intrastromal tunnels are created superiorly and inferiorly, where tiny acrylic half-rings are placed. The thickness of the ring segments may vary in accordance with the amount of corneal flattening required in the keratoconic cornea. Boxer-Wachler and colleagues13 reported 74 eyes in 50 patients with Intacs (Addition Technology, Inc., Des Plaines, Ill.) intrastromal rings. Over 9 months' to 2 years' follow-up, best-corrected visual acuity improved from an average of 20/50 to 20/32, which reflects a change of two lines of acuity. Visual improvement was noted in patients with and without corneal scarring. Corneal topography demonstrated a significant reduction in the steepness and symmetry of the cone. Long-term follow-up is required to determine the overall safety and efficacy of this procedure.
References
1. Kennedy RH, Bourne WM, Dyer JA. A 48-year clinical and epidemiologic study of keratoconus. Am J Ophthalmol. 1986;101:267-273.
2. Sawagamuchi S, Yue BYT, Sugar J, Giljoy JE. Lysosomal abnormalities in keratoconus. Arch Ophthalmol. 1989;107:1507-1510.
3. Sawagamuchi S, Twinning SS, Yue BY, et al. Alpha 2 macroglobulin levels in normal human and keratoconus corneas. Invest Ophthalmol Vis Sci. 1994;35:4008-4014.
4. Wilson SE, He YG, Weng J, et al. Epithelial injury induces keratocyte apoptosis: Hypothesized role for the interleukin 1 system in the modulation of corneal tissue and wound healing. Exp Eye Res. 1996;62:325-337.
5. Kenney MC, Brown DJ, Rajeev B. Everett Kinsey Lecture. The elusive causes of keratoconus: A working hypothesis. CLAO J. 2000;26(1):10-13.
5. Rabinowitz YS, McDonnell PJ. Computer-assisted corneal topography in keratoconus. Refract Corneal Surg. 1989;5:400-406.
6. Rabinowitz YS, Garbus JJ, Garbus C, McDonnell PJ. Contact lens selection for keratoconus using a computer-assisted videophotokeratoscope. CLAO J. 1991;17:88-93.
7. Price FW, Whitson WE, Marks RG. Graft survival in four common groups of patients undergoing penetrating keratoplasty. Ophthalmology. 1991;98:322-328.
8. Sharif KW, Casey TA. Penetrating keratoplasty for keratoconus: Complications and long-term success. Br J Ophthalmol. 1991;75:142-146.
9. Tuft SJ, Gregory WM, Davidson CR. Bilateral penetrating keratoplasty for keratoconus. Ophthalmology. 1995;102:462-468.
10. Abelson MB, Collin HB, Gillete TE, Dohlman CH. Recurrent keratoconus after keratoplasty. Am J Ophthalmol. 1980;90:672-676.
11. Waller SG, Steinert RF, Wagoner MD. Long-term results of epikeratoplasty for keratoconus. Cornea. 1995;14:84-88.
12. Mortensen J, Ohrstrom A. Excimer laser photorefractive keratectomy for treatment of keratoconus. J Refract Corneal Surg. 1994;10:368-372.
13. Boxer-Wachler BS, et al. INTACS for keratoconus in corneas with and without scarring. American Academy of Ophthalmology Annual Meeting, Orlando, Florida, October 2002.